


In this guide16 sections
- Key Points
- What are hooded eyes? Hooded eyelids explained
- How Do I Know If I Have Hooded Eyes?
- Are Hooded Eyes Attractive?
- Hooded eyes vs droopy eyelids (ptosis) — what is the difference?
- When Should You Seek Treatment for Hooded Eyes?
- What Causes Hooded Eyes?
- How to fix hooded eyes without surgery
- How to Fix Hooded Eyes Naturally — What Actually Helps?
- How to Get Rid of Hooded Eyes — Surgical Treatment
- Can Hooded Eyes Return After Surgery?
- Hooded eyelid surgery recovery — what to expect
- Frequently Asked Questions
- Where to read next
- Why Have Blepharoplasty at Centre for Surgery?
- References
Key Points
- What are hooded eyes? Excess upper eyelid skin (dermatochalasis) that folds down from the brow bone over the natural crease, sometimes reaching the lashes.
- Largely inherited: a 2014 study of UK twins estimated that around 61% of the variation in sagging eyelids is genetic; older age, male sex, lighter skin and a higher BMI also raise the risk.[1]
- Makeup and lifestyle measures can disguise hooding, but no exercise, cream or massage removes the skin.
- How to fix hooded eyes: an upper blepharoplasty removes the excess skin, a brow lift corrects a low brow, and many people benefit from both.
- Not only cosmetic: marked hooding can restrict the upper field of vision and cause eye strain and brow ache, and surgery measurably widens the visual field.[2]
Hooded eyes are one of the most frequently treated concerns at Centre for Surgery in London. Characterised by excess skin that droops from the brow bone down towards or over the upper lash line, hooded eyes can make the eyes appear smaller, heavier, and more tired than the person actually feels. For many people, this is a long-standing source of self-consciousness — and for some, the drooping is pronounced enough to begin restricting the upper visual field, making it a functional concern as much as a cosmetic one.
The reassuring news is that eyelid surgery — blepharoplasty — can address hooded eyes very effectively. Hooded eye surgery produces results that are natural, long-lasting, and in most cases transformative. Understanding what hooded eyes are, what causes them, and what treatment options are available will help you make the most informed decision about your next steps. Hooded eyes are a different eyelid concern from a monolid — an eyelid without a visible upper crease — though the two are sometimes confused; we cover that distinction separately.
What are hooded eyes? Hooded eyelids explained
Hooded eyes — also called hooded eyelids — describe a condition where excess skin folds over the upper eyelid and encroaches on the orbital space above the lash line. The clinical term for the excess upper eyelid skin itself is dermatochalasis, and you will see it used on referral letters and in surgical notes; hooded eyes and hooded eyelids are the everyday descriptions of the same finding. This excess skin comes from the upper eyelid itself and from the area beneath the brow bone. When present to a significant degree, it creates a characteristic visual effect where the visible portion of the upper eyelid — the mobile, coloured part — is partly or largely obscured by the overhanging skin.
From the front, hooded eyes give the face a slightly heavy, brooding, or tired expression. Makeup can become difficult to apply effectively, as eyeshadow applied to the upper lid is hidden beneath the fold of skin when the eyes are open. Many people with pronounced hooding also find themselves unconsciously raising their eyebrows to lift the overhanging skin and improve their visual field — a compensatory habit that can contribute to forehead wrinkles over time.
Hooding is one of several distinct concerns that eyelid surgery can treat, alongside under-eye bags, asymmetry and the absence of a defined crease. It also sits within the wider anatomy of the eye region — the position of the brow above it, the tilt of the outer corner, and the hollowing beneath. Our guides to eye shapes and canthal tilt cover how those features interact, and whether eyelid surgery changes your eye shape answers a question most patients ask at consultation.
How Do I Know If I Have Hooded Eyes?
Two simple self-checks can indicate whether you have hooded eyes:
- The crease test: Open your eyes normally and look straight ahead in a mirror. If the natural crease of your upper eyelid is difficult to see — or entirely hidden beneath overhanging skin — this is a strong indicator of hooded eyes.
- The lash line test: If the skin beneath your brow bone sits close to or touches your upper lash line when your eyes are open, you likely have hooded eyes. People with pronounced hooding often have little or no visible eyelid space between the crease and the lashes.
Hooded eyes exist on a spectrum from very mild — where the crease is slightly obscured — to pronounced, where the overhang covers the majority of the visible eyelid. The degree of hooding is one of the key factors your surgeon will assess at consultation.

Hooded eyes are not a female concern — men present with the same finding, often later and often because the visual field has become obstructed rather than for appearance. The surgical approach is the same, though the amount of skin removed is usually more conservative in men to avoid feminising the brow-lid relationship.

Are Hooded Eyes Attractive?
Hooded eyes are a completely normal and common facial feature — and for many people, an appealing one. The feature is widely considered to give the face a deep-set, expressive quality that photographs well and is associated with a naturally intense gaze.
Whether hooded eyes are a concern worth treating is entirely subjective. Many people live comfortably with hooded eyes throughout their lives and have no desire to change them. Others find that pronounced hooding makes them look consistently tired or older than they feel, affects their confidence, or — in more significant cases — encroaches on their visual field. The decision to seek treatment is a personal one, and a consultation at Centre for Surgery is a no-obligation starting point for exploring your options.
Hooded eyes vs droopy eyelids (ptosis) — what is the difference?
Hooded eyes and droopy eyelids are frequently confused, but they are clinically distinct:

- Hooded eyes are caused by excess skin in the upper eyelid — the skin itself droops, creating the characteristic heavy fold. The eyelid muscle function is normal. This is either a genetic trait or develops with age.
- Ptosis refers to drooping of the eyelid margin itself, caused by weakness or dysfunction of the levator muscle responsible for lifting the eyelid. In ptosis it is the eyelid that droops, not just the skin above it. Ptosis can affect one or both eyes and may be present from birth or develop later.
The distinction matters because the two conditions require different treatment. Upper blepharoplasty addresses excess eyelid skin (hooded eyes); ptosis repair addresses the levator muscle. In some patients, both conditions are present simultaneously. Your surgeon at Centre for Surgery will assess which component — skin laxity, muscle function, brow position, or a combination — is contributing to your eyelid appearance, and recommend the appropriate surgical approach.
When Should You Seek Treatment for Hooded Eyes?
There is no obligation to treat hooded eyes, and many people choose not to. However, treatment is worth considering when one or more of the following apply:
- Visual impairment: If the overhanging skin is encroaching on your upper visual field and affecting activities such as reading, driving, or screen work, this is a functional concern that may warrant surgical correction — and may in some cases qualify for NHS referral or insurance support.
Is hooded eyelid surgery functional or cosmetic?
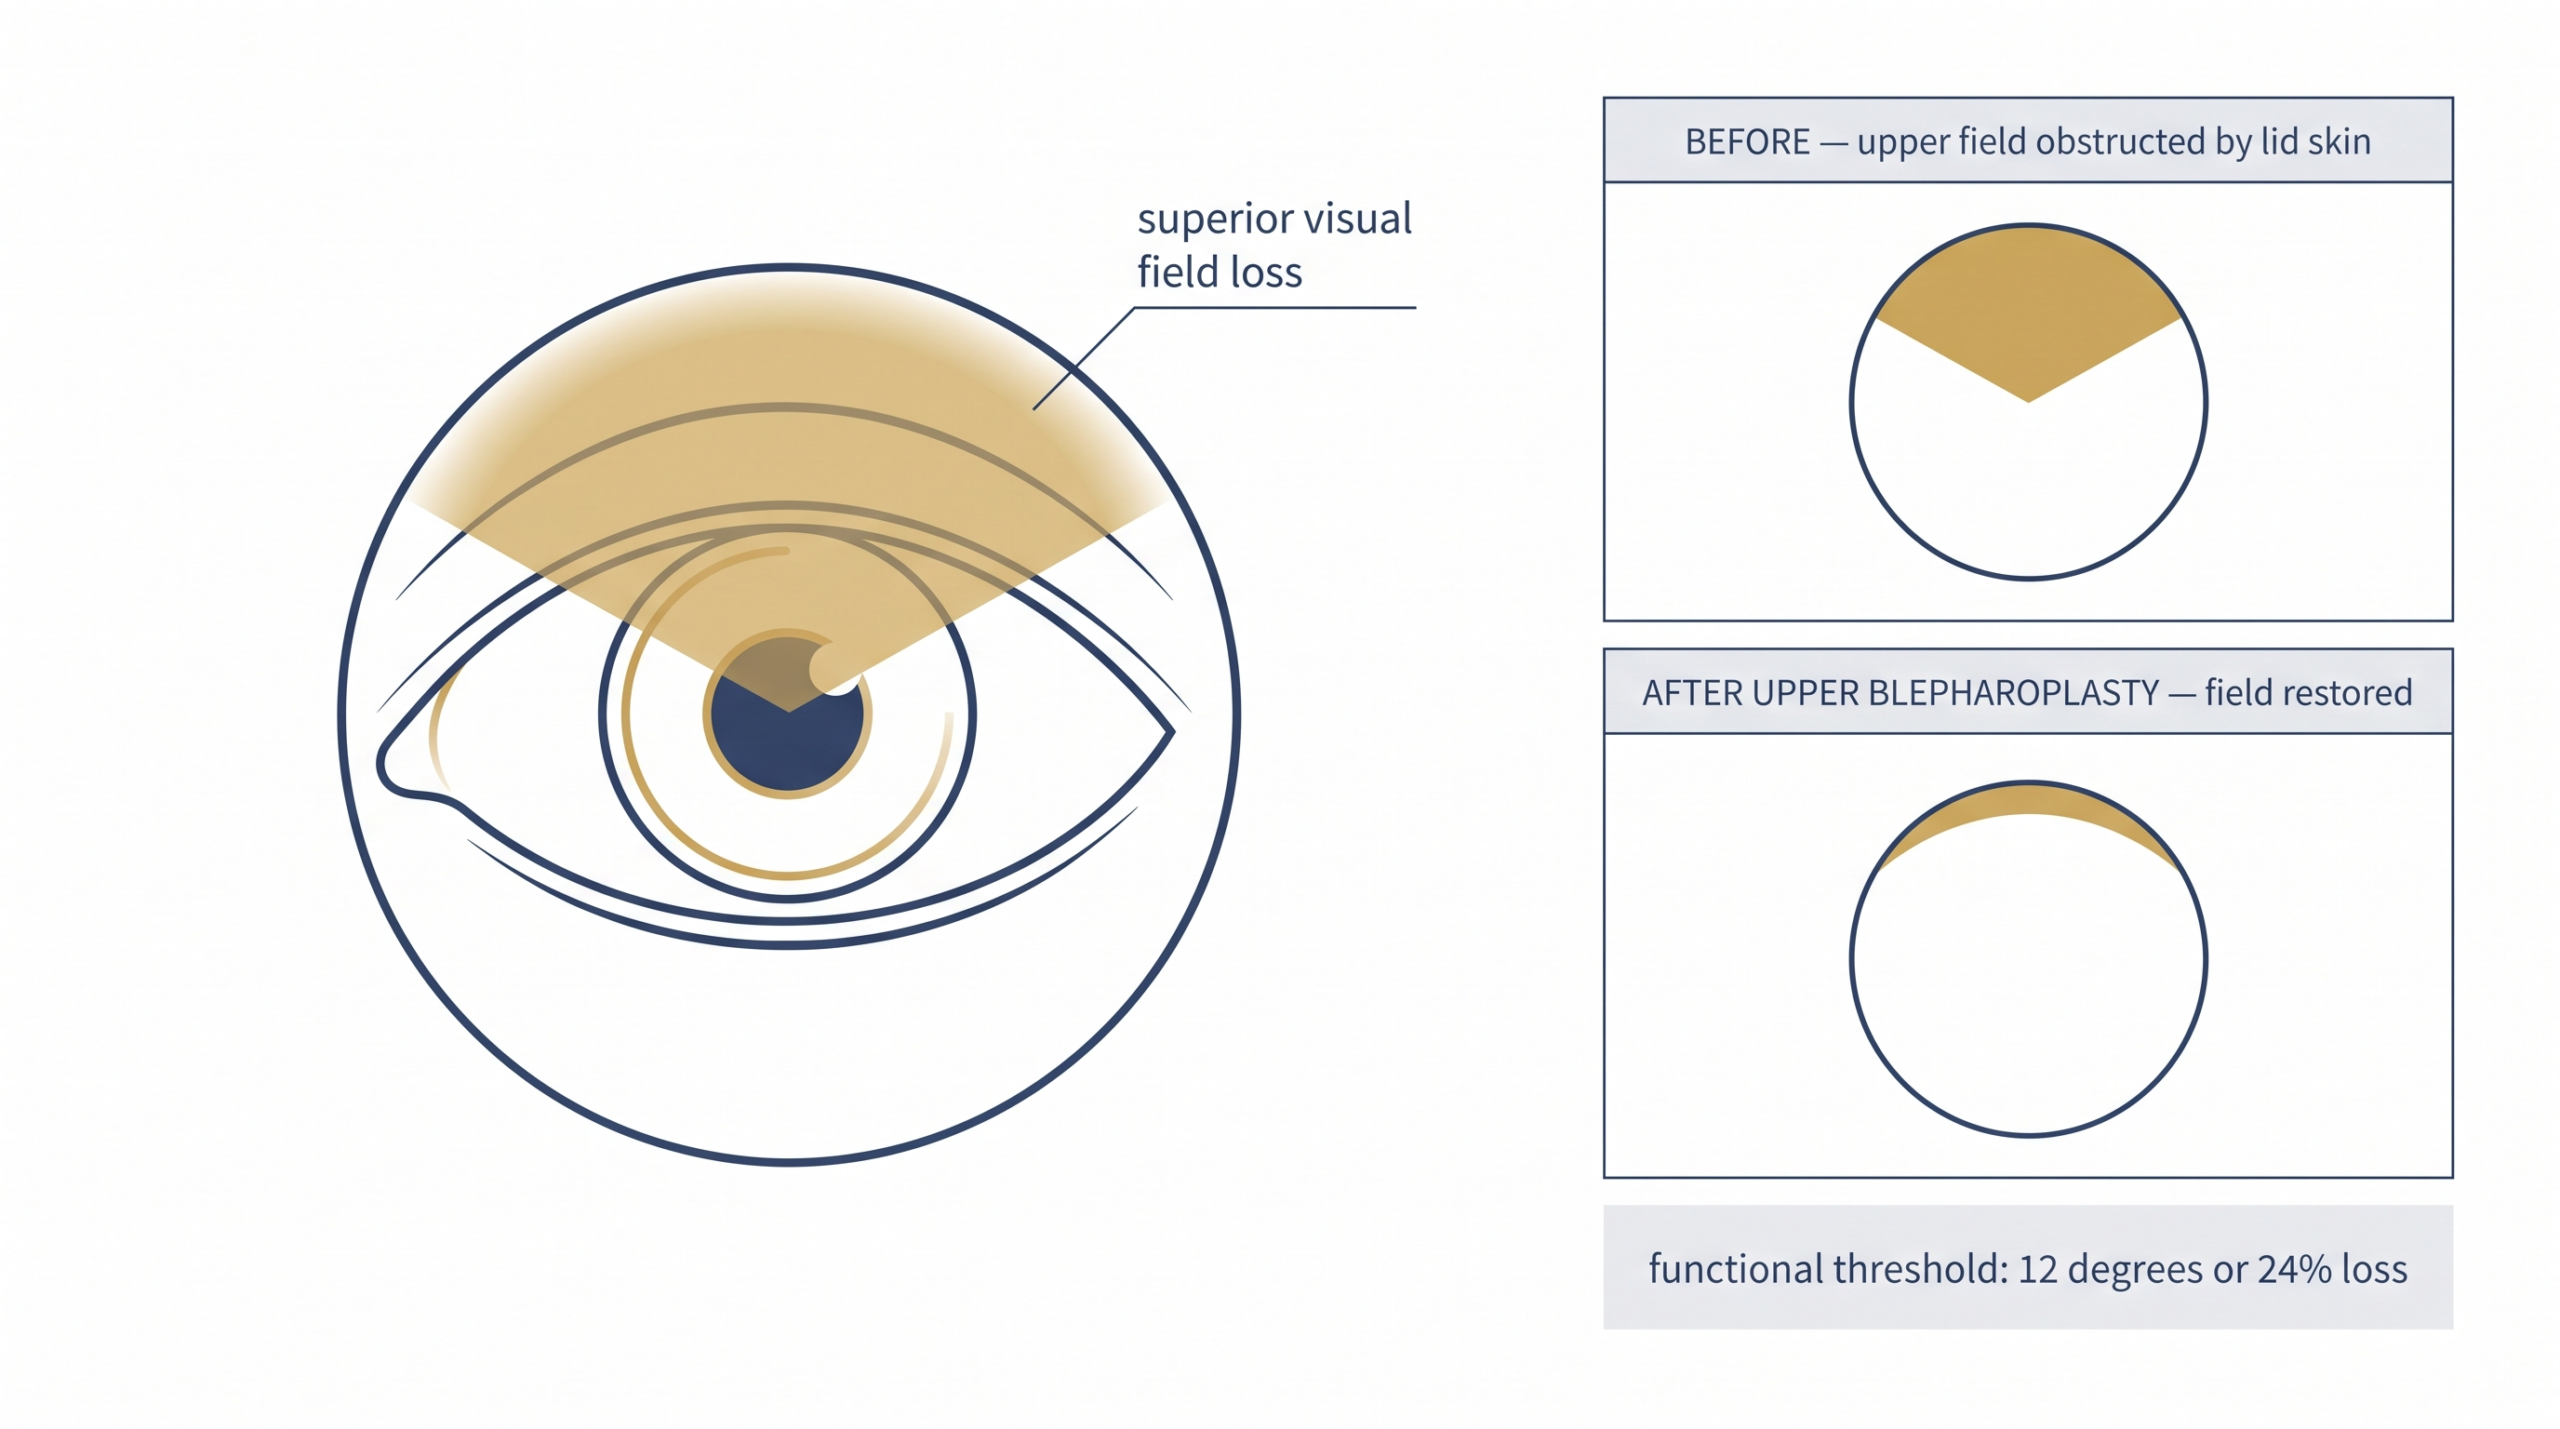
This distinction determines funding, and it is better supported by evidence than most people realise. An American Academy of Ophthalmology assessment published in Ophthalmology ↗ reviewed the evidence and concluded that repairing upper eyelid dermatochalasis produces significant improvement in vision, peripheral vision and quality of life. It set out the preoperative indicators that predict benefit, including superior visual field loss of at least 12 degrees or 24%, a margin reflex distance of 2 mm or less, and a chin-up head tilt adopted to see past the lid.[2]
A UK study from Leicester Royal Infirmary, published in Eye ↗, followed 97 patients across 194 eyes. Among those having blepharoplasty alone, 90.9% showed measurable improvement in the visual field test and 80.6% in visual field height. The authors concluded that dermatochalasis should be considered a functional rather than a cosmetic issue.[3]
Worth knowing if you are being assessed: a prospective study in Orbit ↗ found that preoperative visual field testing underestimated the actual post-surgical improvement by an average of 35%. In other words, the benefit tends to be greater than the test predicts — which matters if a borderline result is being used to decline funding.[4]
Other reasons people seek treatment
- Persistent tired appearance: If you consistently look more tired, heavy, or older than you feel — and this is affecting your confidence in professional or social settings — correction can make a significant and lasting difference.
- Makeup difficulty: If eyeshadow or liner applied to your upper lid disappears beneath the skin fold when your eyes are open, this is a sign of clinically significant hooding.
- Progressive worsening: Hooded eyes caused by ageing tend to worsen gradually. Addressing them earlier generally produces more straightforward results with less skin removal required.
What Causes Hooded Eyes?
Hooded eyes can arise from a combination of different causes, and in many cases more than one factor is contributing simultaneously. Understanding which factors are at play in your particular situation is important in determining the most appropriate treatment.

Genetics
The most common cause of hooded eyes is genetic predisposition. The shape and configuration of the eyelids — including how much skin is present in the upper eyelid and how low the brow naturally sits — are inherited characteristics. If your parents or grandparents had heavy upper eyelids, there is a meaningful probability that you will too, and in many cases the changes begin to appear at a relatively young age — sometimes in the twenties or thirties rather than later in life.
Natural Ageing
Ageing is the second most common cause of hooded eyes. As we age, the skin throughout the body loses collagen and elastin — the structural proteins responsible for its firmness and elasticity. In the eyelids, where the skin is already exceptionally thin, this loss of elasticity is particularly noticeable. The skin becomes increasingly lax, and the natural effect of gravity causes it to descend over the upper eyelid. The fat pads around the orbital rim can also shift with age, further contributing to the heavy, weighty appearance of the upper lids.
Brow Ptosis — Descent of the Brow
An important distinction that must be made at the consultation stage is whether the hooded appearance of the upper lids is caused primarily by excess eyelid skin itself, by descent of the brow bone, or by a combination of both. As the brow descends with age, the weight of the brow tissue is transferred onto the upper eyelid, creating the appearance of excessive skin in the upper lid even where the eyelid skin itself has not significantly changed. This is known as brow ptosis, and in cases where it is the primary driver of the hooded appearance, a brow lift rather than — or in addition to — blepharoplasty may be the more appropriate solution.
Your surgeon at Centre for Surgery will assess the relative contributions of excess eyelid skin and brow position during your consultation, and recommend the most appropriate surgical approach based on your specific anatomy.
Eye Injuries and Previous Surgery
Physical trauma to the orbital region — including fractures, deep lacerations, or significant blunt force injury — can occasionally alter the position and appearance of the eyelids. Previous surgery in and around the eye area can also result in scarring or altered tissue tension that contributes to a hooded appearance. These cases are typically more complex and require a highly individualised assessment.
Medical Conditions
Certain medical conditions can affect the eyelids and contribute to drooping or heaviness. Myasthenia gravis — a neuromuscular condition affecting voluntary muscle control — can cause bilateral or asymmetric eyelid drooping that worsens with fatigue. Horner syndrome, third nerve palsy, and Bell’s palsy and other forms of facial palsy can all affect the nerves supplying the eyelid muscles and produce ptosis. Thyroid eye disease is another well-recognised cause of eyelid changes. If there is any possibility that a medical condition is contributing to your eyelid appearance, your surgeon will refer you for appropriate investigation before any surgical intervention is planned.
How to fix hooded eyes without surgery
For patients with mild hooding who are not yet ready for surgery, or who wish to explore non-surgical options first, there are several treatments that can produce a degree of improvement. It is important to approach these with realistic expectations, as their effects are limited in comparison to surgery and are temporary.
Anti-Wrinkle Injections — Brow Lift Effect
Anti-wrinkle injections (muscle relaxant injections) can be used to subtly elevate the brow by relaxing the muscles that pull it downwards. When placed accurately by an experienced injector, this creates a modest lifting effect that can temporarily reduce the degree of upper eyelid hooding. The effect typically lasts three to four months and requires maintenance. It is most useful in younger patients with mild hooding caused primarily by brow descent rather than significant excess eyelid skin.
Dermal Fillers
Dermal fillers placed along the brow bone or in the temples can add volume that gently lifts the brow and reduces the drooping appearance of the upper eyelids. Like anti-wrinkle injections, this is a temporary measure that requires periodic maintenance and is most effective in cases of mild hooding. It is not suitable for patients with significant excess skin.
Ptosis Crutches
In cases where eyelid drooping is genuinely causing visual impairment and surgery is either not appropriate or not yet desired, ptosis crutches — small devices attached to the frames of spectacles that physically support the upper eyelid — can provide a practical functional solution. They are not a cosmetic treatment and do not improve the appearance of the eyelids, but they can help with vision in appropriate cases.
For patients with mild hooding or those considering a temporary improvement, these non-surgical options can be discussed during your consultation at Centre for Surgery. However, for patients with moderate to significant hooding, surgery is the only option that produces reliable, long-lasting, and meaningfully visible improvement.
How to Fix Hooded Eyes Naturally — What Actually Helps?
Searches for natural fixes are common, so it is worth being clear about what lifestyle measures can and cannot do. Hooding is structural: surplus upper eyelid skin, often combined with a lowering brow. No exercise, massage, cream or diet removes that skin once it has formed.
What the research does show is what makes hooding more likely. A 2014 study of more than 7,700 adults from the Rotterdam Study and TwinsUK, published in JAMA Dermatology ↗, found that older age, male sex, lighter skin colour and a higher body mass index were each independently linked to sagging upper eyelids, with current smoking a borderline factor, and estimated that around 61% of the variation is inherited.[1]
- Sun protection: daily SPF and wraparound sunglasses limit ultraviolet damage to the thin eyelid skin and reduce squinting.
- Not smoking and a stable weight: both are modifiable factors from the study above.
- Eye and brow exercises: there is no good-quality evidence that they reduce hooding, and constant brow-raising can deepen forehead lines.
- Cold compresses, sleep and less salt: these ease morning puffiness, which makes mild hooding look worse, but the effect lasts hours rather than months.
When the fold rests on your lashes, or you catch yourself lifting your brows to see, natural measures will not change it. That is the point to consider an upper blepharoplasty or a brow lift.
How to Get Rid of Hooded Eyes — Surgical Treatment
The most effective and permanent solution for hooded eyes is surgical. Depending on the nature and cause of the hooding, two main surgical options are available: upper blepharoplasty and brow lift surgery. In many cases, the optimal outcome requires a combination of both.

Upper Blepharoplasty — Hooded Eyelid Surgery
Upper blepharoplasty involves the precise removal of excess skin from the upper eyelid, with or without removal or redistribution of a small amount of the underlying orbital fat. The incision is placed within the natural crease of the upper eyelid, ensuring that the resulting scar is concealed within the fold and essentially invisible once healed.
The amount of skin removed is carefully measured and planned to achieve a natural, open result without over-correction. Over-removal of upper eyelid skin — leaving insufficient skin to close the eye properly — is one of the most serious complications of blepharoplasty (and the one UK surgeons now see most often after low-cost blepharoplasty abroad), and it is a risk that is virtually eliminated when the procedure is performed by an experienced specialist. The goal is always to create a rested, refreshed, and naturally youthful appearance rather than a surprised or artificial look.

More cases are shown in our blepharoplasty before and after gallery, photographed to a consistent standard so the comparisons mean something.
Upper blepharoplasty alone is the most appropriate solution when excess eyelid skin is the primary cause of the hooded appearance and when the brow position is satisfactory. It is typically performed as a day-case procedure, usually under local anaesthetic with sedation, or under TIVA where it is combined with a brow lift or other procedures. It takes approximately one to one and a half hours and produces results that last a decade or more in most patients.
Where the lower lids are also a concern, that is a separate operation with a different risk profile — our comparison of upper versus lower blepharoplasty explains why the two are not interchangeable, and recovery after eyelid surgery sets out what the fortnight afterwards actually involves.
Brow Lift Surgery
When brow ptosis is a significant contributing factor to the hooded appearance — either alone or in combination with excess eyelid skin — a brow lift may be recommended. Brow lift surgery elevates the brow back towards its natural, more youthful position, and in doing so reduces the weight of brow tissue being transferred onto the upper eyelid. This can dramatically improve the hooded appearance even without removing any upper eyelid skin directly.
Several different brow lift techniques are available, each suited to different anatomical presentations and patient preferences. These include the temporal brow lift, which focuses on the outer third of the brow; the endoscopic brow lift, a minimally invasive technique using small incisions and a camera; and the Gliding Brow Lift, an advanced technique that repositions the entire brow with minimal visible scarring. Your surgeon will discuss the relative merits of each approach during your consultation.
In many patients, combining an upper blepharoplasty with a brow lift in the same surgical session produces the most complete and harmonious result, addressing both the excess eyelid skin and the brow descent simultaneously with a single recovery period.
Not every patient needs both, and a proportion who arrive asking for blepharoplasty turn out to be better served by brow work alone. Where the brow tail specifically is heavy, a droopy eyebrow is the concern rather than the eyelid, and lifting it addresses the hooding without touching the lid at all.
Can Hooded Eyes Return After Surgery?
Upper blepharoplasty produces long-lasting results — typically ten or more years before any significant recurrence of excess eyelid skin becomes apparent. Lower blepharoplasty addressing fat prolapse is often considered permanent, as the removed fat does not regenerate. However, the natural ageing process continues following surgery, and over time new laxity may develop in the eyelid skin. Some patients choose to have a minor revision procedure many years after their original blepharoplasty, though many find that a single procedure is sufficient for the long term.
The longevity of results from a brow lift also varies depending on the technique used, the extent of correction achieved, and the individual patient’s ongoing ageing pattern. Your surgeon will discuss realistic expectations for longevity at your consultation.
Hooded eyelid surgery recovery — what to expect
Recovery from upper blepharoplasty typically involves one to two weeks of visible bruising and swelling around the eyes, after which most patients are comfortable returning to work and social activities. The sutures are removed at around five to seven days. Final results continue to refine over the following months as residual swelling resolves fully.
Combined upper blepharoplasty and brow lift surgery has a slightly longer recovery due to the additional brow work, and patients typically take two weeks off before resuming most normal activities. Strenuous exercise and activity that raises the heart rate significantly should be avoided for at least four weeks following any eyelid or brow surgery.
Frequently Asked Questions
Will upper blepharoplasty completely fix my hooded eyes?
In cases where excess upper eyelid skin is the primary cause of hooding and the brow position is satisfactory, upper blepharoplasty alone typically produces an excellent and comprehensive correction. Where brow descent is also contributing, a combined approach with brow lift surgery may be needed for the best result.
How do I know if I need a blepharoplasty or a brow lift?
This is determined at your consultation through a clinical assessment. Your surgeon will evaluate the position of your brow, the amount of excess skin in the upper eyelid, and the relative contribution of each to the hooded appearance. In many cases, both procedures are beneficial, and your surgeon will provide a clear recommendation tailored to your anatomy.
Is the surgery painful?
No. Upper blepharoplasty is usually performed under local anaesthetic with sedation — the eyelid is completely numb and you are relaxed but comfortable. Brow lift surgery, and cases where the two are combined, are performed under TIVA with a consultant anaesthetist, meaning you are fully asleep. Your surgeon will confirm which applies to you at consultation. Post-operatively, most patients find any discomfort is mild and well managed with standard over-the-counter pain relief.
Can hooded eyes cause vision problems?
Yes. In more pronounced cases, excess upper eyelid skin can encroach on the upper visual field, restricting peripheral vision and making certain activities such as reading and driving more difficult. When hooded eyes are causing functional visual impairment, the treatment may be eligible for insurance coverage or NHS referral, depending on the degree of impairment. The benefit goes beyond the visual field test: a 2026 review in Orbit ↗ found that upper blepharoplasty also improves eyelid heaviness, tearing, contrast sensitivity and headache-related quality of life.[5]
What is the number one trick for hooded eyes?
For makeup, apply eyeshadow with your eyes open and looking straight ahead in the mirror, not closed. Place a soft matte shade slightly above your natural crease so it stays visible above the fold, keep shimmer to the centre of the lid, and use a thin line tight to the upper lashes rather than a thick wing. Curling the lashes and grooming the tail of the brow upwards also open the eye. These tricks disguise hooding but do not remove skin; where the fold reaches the lashes, an upper blepharoplasty is the lasting fix.
Do hooded eyes get more hooded as you age?
Usually, yes. Eyelid skin is the thinnest on the body, and as collagen and elastin decline it stretches, while the brow tends to sit lower and the fat around the eye shifts forward. In the Rotterdam Study, age was a significant independent risk factor for sagging upper eyelids (Jacobs et al., JAMA Dermatology 2014 ↗)[1], so hooding that is mild in early adulthood commonly becomes more pronounced in middle age.
Is it rare to have hooded eyes?
No. Some degree of hooding is very common and is often an inherited feature rather than a sign of ageing. When researchers graded eyelid photographs of 5,578 adults with an average age of 67, 17.8% had moderate or severe sagging, with upper eyelid skin hanging over the lashes; among 2,186 UK twins with an average age of 53, the figure was 15.6% (Jacobs et al., 2014)[1]. Those figures count only the more marked cases, not milder hooding that simply hides the crease.
What ethnicity is most likely to have hooded eyes?
Hooding is seen in every ethnic group. Many people of East and South-East Asian heritage have a low or absent upper eyelid crease, which can look hooded but is a different anatomy and is treated with Asian blepharoplasty rather than skin removal alone. Age-related hooding is a separate matter: in a large European and UK study, lighter skin colour was independently linked to sagging upper eyelids (Jacobs et al., 2014)[1].
How much does treatment for hooded eyes cost?
Cost depends on whether you need upper blepharoplasty, a brow lift, or both — so a single figure would be misleading. Our blepharoplasty cost guide sets out current prices by procedure and what each quote includes. Your exact price is confirmed in writing after consultation, and finance is available, subject to status.
What’s the difference between hooded eyes and normal eyes?
With your eyes open and looking straight ahead, a non-hooded upper eyelid shows a visible band of lid skin between the lashes and the crease. In hooded eyes, a fold of skin from the brow area hangs down over that crease, so little or none of the mobile lid shows and eyeshadow is hidden. The eyelid margin itself still sits in its normal position, which is what separates hooded eyelids from droopy eyelids. Hooding is a normal variation, often inherited, and only needs treatment if it bothers you or starts to weigh on your vision.
How do you fix upper eyelid exposure?
Upper eyelid exposure is how much lid skin shows between the lashes and the crease when your eyes are open, and hooding reduces it. Make-up techniques can create the illusion of more exposure, and anti-wrinkle injections can lift the tail of the brow slightly for a few months. For a lasting change, upper blepharoplasty removes the overhanging skin so the lid shows again, and a brow lift helps where a low brow is pushing skin down. Which you need depends on where the excess comes from, which is assessed at consultation.
What could be causing my swollen hooded eyes?
Eyelids that suddenly look puffier and more hooded are usually swollen rather than permanently changed. Common causes include fluid after sleep, salty food or alcohol, allergies such as hay fever or a reaction to cosmetics, and inflammation or infection such as blepharitis or a stye, as the NHS guide to eyelid problems ↗ explains. See your GP if swelling lasts more than a few days or comes with gritty, bulging or watery eyes or double vision, as thyroid eye disease can cause this. Painful, red, hot swelling with a fever needs urgent same-day care.
Which muscle is responsible for eyelid elevation?
The upper eyelid is lifted mainly by the levator palpebrae superioris muscle, helped by a small smooth muscle beneath it called Müller’s muscle. When the levator or its tendon weakens or stretches, the eyelid margin itself sits too low, a condition called ptosis, explained in our guide to droopy eyelids. Hooded eyes are different: the levator works normally, and the problem is excess skin and a lower brow above it, which is why the treatments differ.
Where to read next
If you are weighing up whether to proceed, the most useful next step is usually to look at outcomes and costs together. Our blepharoplasty before and after gallery is photographed to a consistent standard so the comparisons are meaningful, and the blepharoplasty cost guide explains what each quote includes rather than just the headline figure.
Several eyelid concerns are commonly confused with hooding, and it is worth ruling them out before booking anything. Monolid eyes lack a defined upper crease rather than having excess skin over one, and are addressed by Asian blepharoplasty, which differs from standard upper lid surgery in both technique and goal. Droopy eyelids involve the lid margin itself rather than the skin above it, and asymmetry between the two eyes has its own set of causes.
If you would rather avoid surgery for now, our review of non-surgical alternatives to eyelid surgery is candid about how limited those options are for anything beyond mild hooding. And if you have had eyelid surgery elsewhere and are unhappy with the outcome, complications after blepharoplasty and revision eyelid surgery cover what can be corrected.
Why Have Blepharoplasty at Centre for Surgery?
Centre for Surgery is a specialist cosmetic surgery clinic in London for eyelid surgery and facial plastic surgery. Our surgeons have extensive experience performing all types of blepharoplasty and brow lift surgery at our Baker Street surgical facility in Marylebone, central London. All procedures are performed by GMC-registered surgeons, and our clinic is regulated by the Care Quality Commission and rated Good overall.

If you would like to book a consultation for eyelid surgery or brow lift, please contact us today by calling 020 7993 4849, emailing contact@centreforsurgery.com, or completing the contact form below. Finance is available, subject to status.
References
- Jacobs LC, Liu F, Bleyen I, et al. Intrinsic and extrinsic risk factors for sagging eyelids. JAMA Dermatology 2014;150(8):836–843. doi:10.1001/jamadermatol.2014.27 ↗
- Cahill KV, Bradley EA, Meyer DR, et al. Functional indications for upper eyelid ptosis and blepharoplasty surgery: a report by the American Academy of Ophthalmology. Ophthalmology 2011;118(12):2510–2517. doi:10.1016/j.ophtha.2011.09.029 ↗
- Ho SF, Morawski A, Sampath R, Burns J. Modified visual field test for ptosis surgery (Leicester Peripheral Field Test). Eye 2011;25(3):365–369. doi:10.1038/eye.2010.210 ↗
- Pemberton JD, Salter M, Fay A, et al. Investigation of Goldmann perimetry in evaluation of patients for upper eyelid blepharoplasty. Orbit 2018;37(1):48–52. doi:10.1080/01676830.2017.1353115 ↗
- Whitelaw TA. Beyond visual field restriction: reconsidering functional assessment in upper eyelid dermatochalasis. Orbit 2026:1–10. doi:10.1080/01676830.2026.2727052 ↗






