



In this guide18 sections
- Key Points
- What Is a Deviated Septum?
- Deviated Septum Symptoms
- How to Tell If You Have a Deviated Septum
- What Causes a Deviated Septum?
- Why Sprays Sometimes Help
- Septoplasty and Septorhinoplasty
- Is Deviated Septum Surgery Worth It? What the Evidence Shows
- What Are the Benefits of Deviated Septum Surgery?
- What Are the Cons and Risks of Deviated Septum Surgery?
- How Bad Does a Deviated Septum Have to Be for Surgery?
- Is Septoplasty Better With Turbinate Reduction?
- Deviated Septum on the NHS
- Deviated Septum Operation Cost
- Frequently Asked Questions: Deviated Septum
- Nasal Airway Assessment at Centre for Surgery
- References
- Related Reading
Key Points
- A deviated septum is a dividing wall inside the nose that sits off-centre and narrows one side. Some degree of deviation is found in most adults, and most cause no symptoms.
- The typical symptom is a blocked nose that is always worse on the same side, often with mouth breathing, snoring, nosebleeds or crusting.
- Sprays cannot straighten a septum, but steroid sprays and saline can shrink the swollen lining on top of it, and for many people that is enough.
- Is deviated septum surgery worth it? For adults with at least moderate blockage, two randomised trials (BMJ 2023, The Lancet 2019) found septoplasty improved nasal symptoms and quality of life more than sprays. It is not a guaranteed cure, and headaches, tiredness or post-nasal drip on their own are not reliable reasons to operate.
- The main cons are several weeks of recovery, a small risk of bleeding, infection and septal perforation, and the chance that some blockage remains.
- Septoplasty works inside the nose and does not change its shape; septorhinoplasty straightens the septum and reshapes the outside in one operation.
The nasal septum is the wall of bone and cartilage dividing your nose into two passages. When it sits off-centre, one passage is narrower than the other — that is a deviated septum, or deviated nasal septum.
It is extraordinarily common. Studies of unselected adults find some degree of septal deviation in roughly 70 to 80 per cent of people, which makes a perfectly straight septum the exception rather than the rule. Most deviations cause no symptoms at all and need nothing done.
The useful question is therefore not “do I have a deviated septum” — you probably do — but “is mine causing a problem worth fixing”. This guide answers that: what it looks like, how to check at home, why a spray sometimes helps a structural problem, what the NHS will and will not do, and where septoplasty genuinely helps.
What Is a Deviated Septum?

The septum is made of cartilage at the front and thin bone behind, covered on both sides by mucosa. When straight, it divides the nose into two roughly equal channels.
A deviated septum bows, buckles or tilts to one side. The airway on that side narrows; the other side is often wider than normal to compensate. Deviated septum meaning, in plain terms: the dividing wall is off-centre.
What does a deviated septum look like?
From the outside, usually nothing. This surprises people. The septum sits inside the nose, and unless the deviation involves the front portion, the external nose looks entirely normal. A visibly crooked nose is a separate matter, though the two often occur together after injury.
From the inside, it appears as a wall leaning into one passage — sometimes a smooth curve, sometimes a sharp bony ridge. You may glimpse this yourself with a torch, but the front of the nose is the least informative part, and what most people mistake for a deviated septum is a swollen turbinate.
Types of deviation

- C-shaped — a single smooth curve to one side. The most common pattern.
- S-shaped — curving one way high in the nose and the other way lower down, so both sides can be obstructed at different levels.
- Spur — a sharp bony projection into one passage, often where cartilage meets bone. Small spurs can cause disproportionate symptoms and sometimes contact the turbinate, causing headache.
- Caudal deviation — the front portion near the nostrils tilts to one side. This is the type most likely to be visible externally and the most technically demanding to correct.
Deviated Septum Symptoms
- Blocked nose, worse on one side. The cardinal symptom. Usually the same side consistently.
- Difficulty breathing through the nose during exercise, when airflow demand is highest.
- Mouth breathing, particularly at night, with dry mouth and sore throat on waking.
- Snoring and disturbed sleep. See snoring and sleep apnoea.
- Recurrent sinus infections, where the deviation impedes drainage.
- Nosebleeds, because the deviated portion is exposed to airflow and dries out.
- Crusting on the narrowed side.
- Facial pain or headache where a spur contacts the turbinate.
- Post-nasal drip, from altered airflow and impaired clearance.
- Noisy breathing during sleep.
Does a deviated septum cause headaches?
Sometimes, but it is over-diagnosed as a cause. Genuine septal headache is typically caused by a contact point — a spur pressing against the turbinate — producing pain around the eye or temple on that side. Where this is the mechanism, correcting it helps.
Most headaches in people with a deviated septum are not caused by it. Migraine and tension headache are far commoner, and operating on the nose will not improve them. A trial of local anaesthetic applied to the contact point is a useful test before committing to surgery.
Does a deviated septum cause snoring?
It contributes rather than causes. Nasal obstruction increases the effort of breathing in, which encourages mouth breathing and increases collapse of the throat. Correcting a septum reduces snoring in some people and not others, because most snoring originates at the palate rather than the nose.
The clearer benefit is in people who cannot tolerate CPAP because of nasal blockage — there, septal correction can make treatment usable.
Does a deviated septum cause post-nasal drip?
It can contribute by disturbing airflow and mucus clearance, particularly with an associated spur or sinus involvement. But post-nasal drip has many causes — rhinitis, reflux, sinusitis — and septal correction alone often does not resolve it. Worth being realistic about before surgery.
How to Tell If You Have a Deviated Septum

- Block one nostril with a fingertip and breathe in through the other. Then swap.
- Compare. Is one side clearly harder than the other?
- Repeat at different times — morning, evening, after exercise, lying on each side.
The pattern is what matters. If the same side is consistently worse, a structural cause such as the septum is likely. If the blockage swaps sides, that is the normal nasal cycle acting on turbinates — and turbinate swelling, not the septum, is the treatable part.
A further clue: if a decongestant spray temporarily opens the nose completely, much of the obstruction is mucosal rather than structural.
This is a guide, not a diagnosis. Confirmation requires nasal endoscopy.
What Causes a Deviated Septum?
- Developmental. The commonest cause. Cartilage and bone grow at different rates through childhood and adolescence, and the septum buckles as a result. No injury required, and it becomes more apparent in the teens.
- Birth. Compression during delivery can deviate the septum, sometimes noticed only years later.
- Injury. A blow to the nose — sport, a fall, an accident. Often the injury seemed minor and the connection is only made later. See broken nose surgery.
- Untreated septal haematoma. Blood collecting after injury kills the cartilage, causing deviation or collapse into a saddle nose deformity. This needs draining within days.
- Previous nasal surgery. Incomplete correction, or recurrence as cartilage remembers its original shape.
- Ageing. Cartilage weakens and existing deviation can become more pronounced.
Can a deviated septum get worse?
Yes, in two ways. The deviation itself can increase slowly as cartilage weakens with age. More often, the symptoms worsen while the anatomy stays the same — because allergy, rhinitis or turbinate enlargement adds mucosal swelling on top of a fixed narrowing that was previously just about tolerable.
That second mechanism explains why people describe a nose that was fine for decades and then became blocked.
Why Sprays Sometimes Help

This confuses more people than anything else on the subject, and the answer is simple.
A spray cannot straighten your septum. But almost nobody has narrowing from the septum alone. There is usually turbinate swelling or mucosal inflammation on top of it, and that part is treatable. Reduce the swelling and the same deviation may leave a perfectly usable airway.
Practically: if a steroid spray used correctly for six to eight weeks makes a real difference, treating the mucosal component may be all you need. If it makes no difference at all, the obstruction is structural and surgery is the option that will change it.
That trial is worth doing before surgery, and any surgeon who skips it is skipping the cheapest useful test available.
How to fix a deviated septum without surgery
The honest answer: you cannot straighten a septum without surgery. No exercise, device, manipulation or remedy repositions cartilage and bone.
What can help the symptoms:
- Steroid nasal sprays — reduce mucosal swelling. Technique matters: angle outward toward the ear on the same side, using the opposite hand.
- Saline rinsing — clears mucus and improves spray delivery.
- Antihistamines where allergy contributes.
- External nasal strips — these open the nasal valve, not the septum. They help some people considerably, and if they work well that points to nasal valve collapse as part of the problem.
- Sleeping position — lying on the more open side often helps.
Can you push a deviated septum back into place? No, and do not try. Manipulation causes bleeding and can worsen matters. The one exception is a fresh fracture, where an ENT surgeon can sometimes reposition the septum within the first one to two weeks — which is a reason to be seen promptly after a nasal injury.
Septoplasty and Septorhinoplasty

Septoplasty straightens the septum through incisions inside the nose. No external cuts, no change to appearance, no bruising in most cases. Deviated portions of cartilage and bone are removed or repositioned, preserving the lining and enough structure to support the nose — taking too much causes collapse later.
Day case under TIVA, 30 to 60 minutes. Splints may be placed for a week to hold the septum and prevent adhesions.
Septorhinoplasty corrects the septum and reshapes the external nose in one operation. Appropriate where the nose is externally crooked as well, typically after injury, or where you want the appearance changed at the same time.
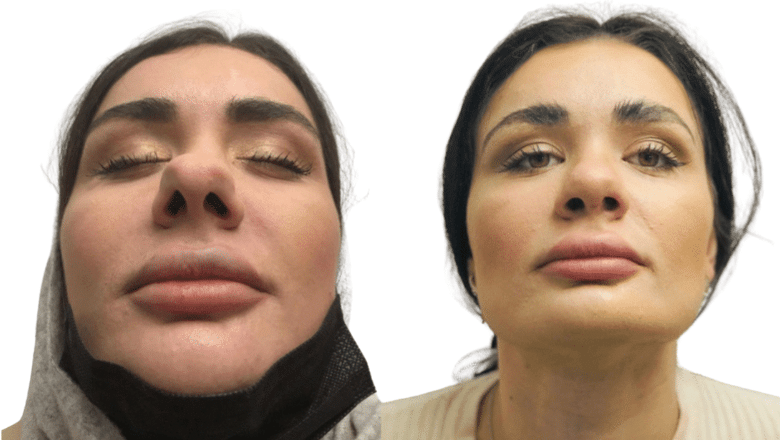
Turbinate reduction is frequently done alongside, because the turbinate on the wider side often enlarges to compensate and remains obstructive once the septum is straightened. See turbinate reduction.
Recovery
Blocked and congested for one to two weeks — frequently worse than before surgery initially, which is normal and catches people out. Splints removed at around a week. Desk work within a week, exercise at three to four weeks. Breathing improves progressively over four to eight weeks as swelling settles.
Does septoplasty change the shape of your nose?
It is not intended to and usually does not. Occasionally a small external change is noticeable where a severe caudal deviation was distorting the external framework. Deliberate shape change requires septorhinoplasty, planned in advance.
Is Deviated Septum Surgery Worth It? What the Evidence Shows
For the right person, the evidence says yes, with some caveats. Until recently, the benefits of septoplasty were questioned because good trials were lacking. That has changed.
In a 2023 UK randomised trial published in the BMJ ↗, 378 adults with a blocked nose and a deviated septum were assigned to septoplasty or to six months of nasal steroid and saline sprays. At six months the average SNOT-22 symptom score was 19.9 after surgery and 39.5 with medical treatment, a difference of about 20 points on a scale where a change of 9 points is considered clinically meaningful. Airflow measurements also improved more in the surgery group[1]. A 2019 Dutch randomised trial in The Lancet ↗ of 203 adults reached a similar conclusion: health-related quality of life was higher after septoplasty than after non-surgical management at 12 months, and the difference was still present at 24 months[2].
A 2025 meta-analysis of three randomised trials ↗ covering 721 people found that septoplasty, with or without turbinate surgery, improved NOSE and SNOT-22 scores at 6 and 12 months compared with non-surgical care. The authors noted that the findings should be interpreted with caution, and that the improvement was not seen at 3 months, which is a reminder that recovery takes time[3]. An NHS economic evaluation run alongside the UK trial concluded that, over 24 months, immediate septoplasty would be cost-effective for people with this problem[4].
These trials studied adults with at least moderate nasal obstruction, so they support surgery for people whose blockage genuinely affects them. They do not show that every deviated septum should be operated on, or that every patient ends up with a perfectly clear nose. In the UK trial, people with worse symptoms before surgery tended to gain the most[1].
What Are the Benefits of Deviated Septum Surgery?
Easier breathing through the nose
The central benefit of septoplasty is improved nasal airflow. Straightening a bent septum widens the narrower passage, so air can travel more evenly through both sides of the nose. People often notice this most when exercising or lying down at night. Our guide to whether you need rhinoplasty or septoplasty explains how the operation is chosen when breathing is the main concern.
Snoring and sleep quality
A blocked nose pushes some people to breathe through the mouth at night, which can contribute to snoring and disturbed sleep. Evidence that nasal surgery improves sleep is encouraging but modest. In a small 2026 prospective study of 32 patients having septoplasty with turbinate reduction, average daytime sleepiness scores improved by 2.7 points three months later, but there was no comparison group, and the improvement did not track with the measured airflow gain[5]. A blocked nose is only one of several causes of snoring and sleep apnoea, so surgery should not be expected to treat either on its own.
Fewer problems with sprays and decongestants
Many people with a deviated septum rely on decongestant sprays that work briefly and can cause rebound congestion if overused. If the blockage is mainly structural, correcting the septum can reduce the need for them, although that depends on whether allergy or swollen turbinates are also involved.
What Are the Cons and Risks of Deviated Septum Surgery?
Septoplasty is a well-established operation, but like any surgery it has drawbacks you should weigh up.
Recovery takes weeks
After surgery, most people have swelling, congestion and mild discomfort for several weeks, and the full benefit to breathing may take longer to appear. This is consistent with the meta-analysis above, in which benefit was clearest at 6 to 12 months rather than at 3 months[3]. Your surgeon will give you advice on rest, nasal care and returning to work and exercise.
Bleeding, infection and perforation
In the UK trial, 7 of 174 patients who had septoplasty (4%) were readmitted to hospital with bleeding, and a further 12% needed antibiotics for an infection[1]. In the Dutch trial, one surgical patient developed a septal abscess and two developed a septal perforation, a hole in the septum[2]. The 2025 meta-analysis reported low overall complication rates, ranging from 0.31% for revision surgery to 4.12% for bleeding and infection[3]. These are small figures, but they are real, and a perforation can cause whistling, crusting or nosebleeds. Our guide to septal perforation explains how it is managed.
It does not always give full relief
Most people report meaningful improvement in nasal breathing. Where it disappoints, the usual reasons are that turbinate enlargement was not addressed, that nasal valve collapse was the real problem, or that expectations included resolving snoring or post-nasal drip that had other causes. Nasal obstruction is also subjective, and the size of the bend does not always match how blocked a person feels, so some people still feel congested after a technically successful operation. The UK trial found that people with milder symptoms before surgery gained less[1]. A small proportion have residual or recurrent deviation, as cartilage has memory; revision is possible but more complex. Read more about whether nose surgery can help nasal allergies.
Your sense of smell
Loss of smell is uncommon, but it is worth knowing about. A 2026 systematic review of 102 studies and 16,072 patients found that surgery-induced loss of smell occurred in around 2.7% of cases across septoplasty, turbinate surgery and septorhinoplasty, although overall the number of people with reduced smell fell after surgery, from 22.2% to 14.5%[6]. Our article on whether nose surgery affects smell or taste covers this in more detail.
How Bad Does a Deviated Septum Have to Be for Surgery?
There is no single threshold. The decision depends mostly on how much the blockage affects your life rather than on how bent the septum looks, and a small deviation can feel very obstructive to one person while a larger one barely bothers another. The trials above recruited people with at least moderate symptoms on a standard questionnaire (a NOSE score above 30), which gives a sense of the level at which surgery was shown to help[1].
A sensible general guide is that surgery is worth discussing if one side is consistently blocked, the septum can be seen to be bent on examination, symptoms have lasted for months, and treatment with a steroid spray and saline has not been enough. If you are unsure, the first step is an examination of the inside of the nose.
The nasal valve and your septum
The internal nasal valve, the narrowest part of the airway at the junction of the upper lateral cartilage and the septum, matters here. Its angle is often quoted in textbooks as around 10 to 15 degrees, a figure referred to in a 2018 endoscopic study in International Forum of Allergy & Rhinology ↗, which also found a wider average angle of about 24 to 25 degrees in a small group of Mexican-Hispanic adults without symptoms[7]. A 2023 study of 75 patients with septal deviation, in which the textbook range was given as 9 to 15 degrees, found that most had an angle below 9 degrees and argued that the commonly quoted normal range should be questioned[8]. In short, valve angles vary between people, and the number alone does not decide who needs surgery.
If the valve itself is narrowed, septoplasty may not fix the problem and additional techniques such as cartilage grafting may be needed.
Is Septoplasty Better With Turbinate Reduction?
Many people with a deviated septum also have enlarged inferior turbinates, the ridges of tissue along the side wall of the nose that swell and shrink. When the turbinates are swollen, straightening the septum alone may leave the nose partly blocked, which is why surgeons sometimes combine the two operations. The Dutch trial and the meta-analysis above both included patients who had septoplasty with or without turbinate surgery[2][3]. Whether turbinate reduction is advisable depends on your examination findings. Our guide to the pros and cons of turbinate reduction with septoplasty explains how the decision is made.
Deviated Septum on the NHS
Septoplasty is available on the NHS, but access has tightened considerably.
Most integrated care boards apply threshold criteria under the Evidence Based Interventions programme — typically requiring documented nasal obstruction significantly affecting quality of life, a confirmed deviation on examination, and a failed trial of medical treatment first, usually a steroid spray for a defined period.
Purely cosmetic nasal surgery is not funded. Where the septum is being corrected for breathing but you also want the external shape changed, the cosmetic element is not covered.
Your GP is the route to referral. Waiting times vary widely by area — deviated septum NHS waiting list times of a year or more are not unusual for a procedure classified as routine, which is the main reason people consider going privately.
Deviated Septum Operation Cost
Private cost depends on whether septoplasty alone is required or whether turbinate reduction or external correction is included, and on the anaesthetic. Septorhinoplasty costs more than septoplasty because it addresses both function and appearance.
Your exact cost is confirmed in writing after in-person consultation and examination. Finance is available through Chrysalis Finance, subject to status — see our finance options.
Frequently Asked Questions: Deviated Septum
What is a deviated septum?
The wall dividing the two sides of the nose sitting off-centre, narrowing one nasal passage. It affects around 70 to 80 per cent of people to some degree, and most cause no symptoms.
What does a deviated septum look like?
From the outside, usually nothing at all — it sits inside the nose. Internally it appears as a wall bowing into one passage, either as a smooth curve or a sharp bony ridge. A visibly crooked nose is a separate issue that often coexists.
How do you know if you have a deviated septum?
Block one nostril at a time and compare, repeating at different times of day. If the same side is consistently worse, a structural cause is likely. Blockage that swaps sides is usually the normal nasal cycle affecting the turbinates. Endoscopy confirms it.
What causes a deviated septum?
Most commonly uneven growth of cartilage and bone during childhood and adolescence, with no injury involved. Also birth trauma, nasal injury, untreated septal haematoma, previous surgery, and age-related cartilage weakening.
Is a deviated septum serious?
Usually not. Most cause no symptoms and need nothing. It becomes worth treating when it obstructs breathing enough to affect sleep, exercise or quality of life, or contributes to recurrent sinus infections or nosebleeds.
How common is a deviated septum?
Very. Studies of unselected adults find some degree of deviation in roughly 70 to 80 per cent of people. A perfectly straight septum is the exception.
What is a minor or slightly deviated septum?
A small off-centre position causing little or no obstruction. Extremely common and generally needs no treatment. Symptoms usually appear only when mucosal swelling from allergy or rhinitis is added on top.
Can a deviated septum get worse?
The deviation can increase slowly as cartilage weakens with age. More often the symptoms worsen while the anatomy stays the same, because allergy or turbinate enlargement adds swelling to a fixed narrowing.
Can you fix a deviated septum without surgery?
You cannot straighten it without surgery. Steroid sprays, saline rinsing, antihistamines and nasal strips can improve the symptoms by reducing swelling or supporting the nasal valve, and for many people that is enough.
Can you push a deviated septum back into place?
No, and attempting it causes bleeding and can worsen things. The exception is a fresh fracture, where an ENT surgeon may reposition the septum within the first week or two — another reason to be seen promptly after a nasal injury.
Do nasal strips help a deviated septum?
They open the nasal valve rather than the septum, but many people find them genuinely helpful. If a strip works well, nasal valve collapse is probably contributing, and that is worth assessing.
Does a deviated septum cause snoring?
It contributes rather than causes. Nasal obstruction increases breathing effort and encourages mouth breathing, but most snoring originates at the palate. Correction helps some people and not others.
Does a deviated septum cause headaches?
Sometimes, where a spur contacts the turbinate, typically causing pain around the eye or temple on that side. Most headaches in people with a deviated septum have other causes and will not improve with surgery.
Does septoplasty change the shape of your nose?
It is not designed to and usually does not. A small external change is occasionally noticeable where severe front-end deviation was distorting the framework. Deliberate shape change requires septorhinoplasty.
Is septoplasty available on the NHS?
Yes, subject to threshold criteria — documented obstruction affecting quality of life, confirmed deviation, and a failed trial of medical treatment. Waiting times vary considerably. Cosmetic changes are not funded.
How long does recovery take?
Congestion for one to two weeks, often worse than before surgery at first. Splints out at around a week, desk work within a week, exercise at three to four weeks, and breathing settling over four to eight weeks.
Is deviated septum surgery worth it?
For adults with a blocked nose caused by a deviated septum, trials show septoplasty improves symptoms and quality of life more than nasal sprays. It is most worthwhile when symptoms are at least moderate and affect daily life. It cannot promise to remove every symptom.
Is bleeding after septoplasty normal?
Light oozing of blood in the first few days is common. Heavier bleeding is not routine: in the UK trial, around 4% of patients were readmitted to hospital with bleeding. If bleeding is heavy or does not settle, contact your surgical team straight away.
What can happen if a deviated septum is left untreated?
Often nothing: a bent septum that causes no symptoms does not need treatment. If it does cause a persistently blocked nostril, mouth breathing or nosebleeds, these symptoms may continue, and some people try sprays first. Treatment is a choice based on how much the symptoms bother you.
Can you smell with a deviated septum?
Yes, many people can. A heavily blocked passage can reduce how much air reaches the smell area at the top of the nose, so smell may be duller when you are congested. After nose surgery, a review of 16,072 patients found that the number of people with reduced smell fell overall, though a small proportion lost smell[6].
Can deviated septum surgery fail?
Some people are left with a degree of blockage. The 2025 meta-analysis reported a low revision rate of 0.31%, but not everyone who is dissatisfied has repeat surgery[3]. Allergy, swollen turbinates and nasal valve narrowing are common reasons breathing stays limited, so finding the true cause before surgery matters.
Can a deviated septum come back after surgery?
Surgeons aim to hold the septum in a more central position, but the trials above did not set out to measure how often a bend returns. A new injury to the nose can move the septum again, and cartilage can shift as it heals, so persistent or returning blockage is worth having re-examined.
Nasal Airway Assessment at Centre for Surgery
Assessment begins with establishing whether the septum is actually the problem, because most obstructed noses have more than one cause and the septum is often not the dominant one.
Examination includes nasal endoscopy to assess the septum, turbinates, nasal valve and lining together. Where mucosal swelling is a significant part of the picture, we will suggest treating that first — and if a spray resolves it, you will not need surgery.
Our ENT surgeon and rhinologist leads nasal airway assessment. Where surgery is appropriate we will be clear about what it will and will not change, including the specific point that septoplasty reliably improves nasal breathing but does not reliably resolve snoring, headache or post-nasal drip.
All surgery is performed by GMC-registered surgeons at our own day-surgery facility at 95–97 Baker Street, Marylebone. We are regulated by the Care Quality Commission and rated Good overall. We recommend a two-week cooling-off period before any surgery is booked.
Patient reviews
You can read our reviews in full on Google Reviews ↗, or on our own patient reviews page. We are rated 4.6 on Google.
Book a consultation
Phone: 020 7993 4849
Email: contact@centreforsurgery.com
Address: 95–97 Baker Street, Marylebone, London W1U 6RN
Contact us to schedule your consultation
Your initial in-person consultation is £100, redeemable against the cost of surgery if you proceed.
References
- Carrie S, O’Hara J, Fouweather T, et al. Clinical effectiveness of septoplasty versus medical management for nasal airways obstruction: multicentre, open label, randomised controlled trial. BMJ 2023;383:e075445. doi:10.1136/bmj-2023-075445 ↗
- van Egmond MMHT, Rovers MM, Hannink G, et al. Septoplasty with or without concurrent turbinate surgery versus non-surgical management for nasal obstruction in adults with a deviated septum: a pragmatic, randomised controlled trial. Lancet 2019;394(10195):314–321. doi:10.1016/S0140-6736(19)30354-X ↗
- Taha HI, Elgendy MS, Ezz MR, et al. Septoplasty versus non-surgical management for deviated nasal septum: a systematic review and meta-analysis of randomized controlled trials. European Archives of Oto-Rhino-Laryngology 2025;282(2):597–610. doi:10.1007/s00405-024-08937-x ↗
- Homer T, Carrie S, Fouweather T, et al. Cost-effectiveness of immediate septoplasty versus medical management with the option for delayed septoplasty for nasal airways obstruction: a multicentre, open-label, randomised controlled trial. BMJ Open 2026;16(7):e107402. doi:10.1136/bmjopen-2025-107402 ↗
- de Sousa FA, Correia JT, Rios M, et al. Beyond the airway: the impact of septoplasty and turbinate reduction on somnolence and sleep disordered breathing risk, a prospective study. Frontiers in Surgery 2026;13:1828614. doi:10.3389/fsurg.2026.1828614 ↗
- Favreau A, Favier V, Carsuzaa F, et al. Olfactory sequelae of nasal surgeries: a systematic review with meta-analysis. Journal of Otolaryngology – Head & Neck Surgery 2026;55. doi:10.1177/19160216261416371 ↗
- Jasso-Ramírez E, Sánchez y Béjar F, Arcaute Aizpuru F, et al. Nasal valve evaluation in the Mexican-Hispanic (mestizo) nose. International Forum of Allergy & Rhinology 2018;8(4):547–552. doi:10.1002/alr.22091 ↗
- Sunnychan S, Deshmukh P. Association between anterior rhinoscopic/endoscopic assessment of internal nasal valve and various nasal deformities in the rural population of Vidarbha region of India: a cross-sectional study. Cureus 2023;15(3):e35682. doi:10.7759/cureus.35682 ↗
Related Reading
- Septoplasty (deviated septum surgery)
- Septorhinoplasty
- Turbinate reduction surgery
- Nasal turbinates: why they swell
- Nasal valve collapse
- Nasal polyps
- Nasal synechiae (adhesions)
- Saddle nose deformity
- Broken nose surgery
- Snoring and sleep apnoea
- How septoplasty and turbinate reduction help you breathe better
- Nose shapes: the common types







