


In this guide16 sections
- Key Points
- Can Gyno Come Back After Surgery? The Short Answer
- Is Gyno Surgery Permanent?
- How Common Is Gynecomastia Recurrence?
- Can Gyno Come Back After Surgery If You Take Steroids?
- What Else Makes Gyno Come Back? Weight Gain, Medicines and Cannabis
- Why Surgeons Leave Some Tissue Behind
- Chest Not Flat After Gyno Surgery? The Healing Timeline
- Uneven Chest, a Lump or a Hard Area After Gynecomastia Surgery
- Gynecomastia Revision Surgery: When Is It Needed?
- What to Do If You Think Your Gyno Has Come Back
- How to Keep Your Gynecomastia Surgery Results
- Gynecomastia Surgery Before and After
- Frequently Asked Questions
- Why Choose Centre for Surgery for Gynecomastia Surgery?
- References
Key Points
- True recurrence is uncommon. Gland that has been removed does not grow back, and in published series regrowth needing further surgery affects a small minority of men.
- Most “recurrence” is something else. It is usually new fat after weight gain, swelling that has not yet settled, or tissue that was never removed in the first place.
- Steroids are the main exception. In a series of 964 men, steroid users needed revision surgery more than three times as often as non-users.
- Do not judge the result too early. Swelling takes three to six months to settle, and a hard area under the scar is usually scar tissue that softens over the first year.
- A thin layer is left on purpose. Removing every trace of tissue under the nipple causes a crater, so surgeons leave a little behind to keep the chest natural.
- You can protect your result. Keep your weight stable, avoid steroids and cannabis, and get any new swelling checked rather than assuming the worst.
Can gyno come back after surgery? It is one of the first questions men ask before gynecomastia surgery, and an understandable one when you are investing time, money and recovery in getting rid of it. This guide explains how often gynecomastia really comes back, why most changes after surgery are not recurrence, what raises the risk, and what to do if your chest has changed since your operation.
If you have not had surgery yet, our guides to the causes of gynecomastia and whether gyno surgery is worth it are good places to start.
Can Gyno Come Back After Surgery? The Short Answer
Genuine regrowth is uncommon. When men say their gynecomastia has come back, it is usually one of three things, and only one of them is real recurrence:
- New fat over the chest after weight gain. This is pseudogynecomastia, not returned gland, and it is the most common explanation.
- Tissue that was left behind, either deliberately to avoid a hollow chest or because the first operation removed only fat, which becomes more visible as the surrounding fat changes.
- Genuine regrowth of glandular tissue, which needs a new hormonal driver, most often anabolic steroids, cannabis or a medicine started after surgery.
The distinction matters because the treatment is different. Fat responds to weight loss or liposuction; regrown or remaining gland needs to be excised.
Is Gyno Surgery Permanent?
For most men, yes. Gland that has been surgically removed does not regenerate, and fat cells removed by liposuction do not come back. A 2022 systematic review of 53 studies and 5,345 patients in the Journal of Plastic, Reconstructive and Aesthetic Surgery ↗ found that the large majority of men having gynecomastia surgery had idiopathic gynecomastia, with no ongoing cause, and that outcomes were consistently good across surgical techniques.[1]
The result is not a guarantee against future change, though. The tissue left in place, including a thin protective layer under the nipple and the fat elsewhere on the chest, still responds to weight gain and hormones. If whatever caused your gynecomastia is still present, or a new trigger appears, the chest can change again.
How Common Is Gynecomastia Recurrence?
Published recurrence rates depend on the type of tissue, the cause and how recurrence is defined. In a German series of 305 men and 555 operated breasts in the Journal of Plastic Surgery and Hand Surgery ↗, recurrence was 4.7% when the tissue was mature and fibrous, and 12.5% when it was still active, or florid, at the time of surgery.[2] Active tissue is more common in recent gynecomastia, which is one reason surgeons prefer to wait until gyno is established and its cause has been dealt with.
Other series report lower rates. In a 2024 series of 60 men treated with liposuction and gland removal, one man had a recurrence.[3] Rates are consistently higher in men who use steroids, and where the original operation removed fat but left the gland behind.
Can Gyno Come Back After Surgery If You Take Steroids?
Yes, and this is the most common cause of genuine regrowth. In a series of 964 men having gynecomastia surgery in Annals of Plastic Surgery ↗, 11% had used anabolic steroids, and steroid users needed revision surgery 3.8% of the time compared with 1.1% of non-users.[4] In a separate study following 100 men through a single steroid cycle, 19% developed gynecomastia during the cycle.[5]
If you plan to continue using steroids, the remaining tissue under the nipple has the same stimulus it had before, and surgery may not give a lasting result. Our guides to steroid gyno and bodybuilder gynecomastia explain the risks.
What Else Makes Gyno Come Back? Weight Gain, Medicines and Cannabis
- Weight gain. The fat cells removed during surgery are gone, but the remaining ones can enlarge. Significant weight gain puts fat back on the chest, and more body fat means more oestrogen. Keeping your weight stable is the single most useful thing you can do.
- New medicines. Spironolactone, finasteride, some anti-ulcer and heart medicines and anti-androgens can all trigger gynecomastia. If a doctor starts one after your surgery, mention your history. Our guide to finasteride gynecomastia covers the most common one in younger men.
- Cannabis. Cannabis use is linked with gynecomastia. Our article can cannabis cause gynecomastia? looks at the evidence.
- An untreated underlying cause. If gyno started in adulthood, a GP review before surgery can find hormone, thyroid, liver or kidney problems that would otherwise keep driving it.[6]
Why Surgeons Leave Some Tissue Behind
A good gynecomastia operation does not remove every last trace of tissue. A thin, even layer is left beneath the nipple and areola to support it. Removing too much causes a hollow, saucer-shaped dip behind the nipple, known as a crater deformity, which is harder to correct than a little extra fullness.
That remaining tissue is why weight gain or steroids can bring back some fullness. It is also why the chest should look natural and slightly contoured after surgery, not completely flat like a sheet of paper.
Chest Not Flat After Gyno Surgery? The Healing Timeline
Swelling is a normal part of healing, and it is the most common reason men think their gynecomastia has come back. Most of it settles in the first six weeks, but the last of it can take three to six months, and the chest can feel firm or lumpy during that time.
- First two weeks: bruising and swelling are at their peak. A compression vest helps control both.
- Six weeks: most swelling has settled, but the chest may still look fuller than you expected.
- Three months: the shape is close to final. Scar tissue may still feel firm.
- Six to twelve months: the final result. Scar tissue softens and the chest settles.
A chest that does not look flat at eight weeks is usually still swollen, not recurrent. Our guide to gynecomastia recovery covers each stage in detail.
Uneven Chest, a Lump or a Hard Area After Gynecomastia Surgery
Not every change after surgery is recurrence. Three findings come up repeatedly at review, and none of them means the tissue has regrown.
A firm ridge or hard area under the scar. This is usually scar tissue, which forms as part of normal healing and feels firmest between about six weeks and three months before gradually softening over six to twelve months.
An uneven chest. Asymmetry in the early months is common and usually reflects one side settling faster than the other. Most chests are slightly asymmetric to begin with, and surgery does not make them identical. Persistent asymmetry at six months is worth reviewing.
A fluid collection. A soft swelling that appears in the first weeks may be a seroma, a collection of fluid rather than tissue. It is drained rather than operated on, and it is one of the reasons compression garments matter.
Something that is genuinely new, hard and one-sided should be examined rather than assumed to be any of the above. Male breast cancer is uncommon but it exists, and a new one-sided lump needs assessment. Our guide to gynecomastia and breast cancer risk explains what to look for.
Gynecomastia Revision Surgery: When Is It Needed?
Revision is uncommon after a well-planned operation, but a second operation is sometimes the right answer.
Where gland was left behind. If the first operation removed fat by liposuction alone and did not remove the glandular disc, the disc remains and often becomes more obvious once the surrounding fat has gone. This is the most common reason men seek revision, and it is a problem with the original plan rather than recurrence.
Where too much was removed. Over-removal produces a hollow behind the nipple. Correction usually involves fat grafting rather than further removal, and in one series of 148 men, small depressed areas after surgery were successfully corrected with fat grafting.[7]
Where genuine regrowth has occurred because of a new hormonal driver, that driver needs to be identified and stopped before any further surgery.
We regularly see men whose first operation was done elsewhere. If that applies to you, bring any operative notes you have, as knowing what was done makes the assessment more useful. Our guide to gynecomastia revision surgery explains how scar tissue and leftover gland are told apart.
What to Do If You Think Your Gyno Has Come Back
Check the timeline. If your surgery was less than six months ago, it is probably still swelling.
Do the pinch test. Lie on your back and pinch the tissue beneath and around the nipple. Soft tissue that feels the same throughout suggests fat. A firm, rubbery disc that feels different from the tissue around it suggests gland. Our guide to gyno vs chest fat covers this in more detail.
Think about what has changed. Weight gain, a new medicine, a return to steroids or more cannabis use since surgery are all worth mentioning at review.
Book a review with your surgeon. If you had your surgery here, contact us. Assessing a concern after surgery is part of your aftercare, not a new consultation.
How to Keep Your Gynecomastia Surgery Results
- Keep your weight stable after surgery.
- Avoid anabolic steroids, prohormones and SARMs.
- Avoid or cut down on cannabis.
- Tell any doctor who starts a new medicine that you have had gynecomastia.
- Wear your compression vest as advised and let the swelling settle before judging the result.
- Get a GP review before surgery if your gyno started in adulthood, so any cause is found first.
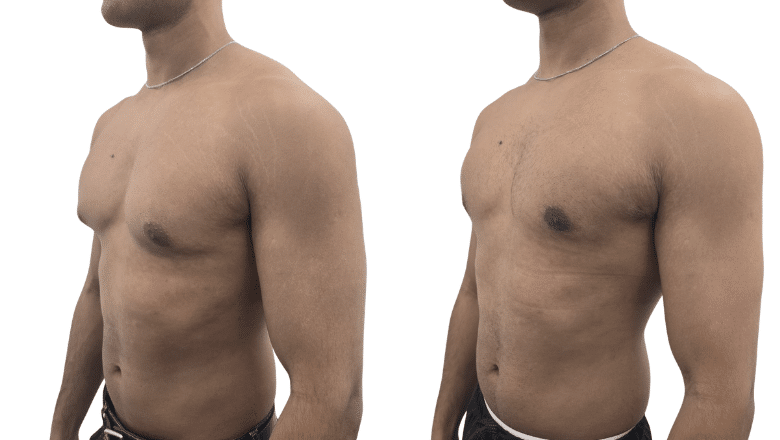
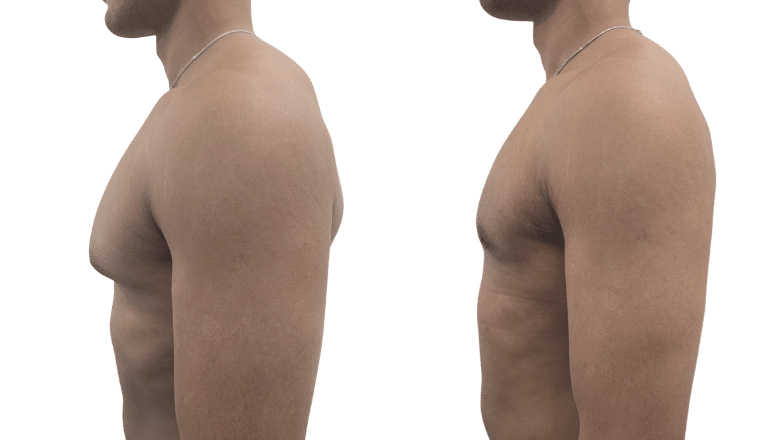
Gynecomastia Surgery Before and After
These are real Centre for Surgery patients. More results are in our gynecomastia before and after photos gallery.
Frequently Asked Questions
Does gyno come back after surgery?
Usually not. Removed gland does not grow back. Most changes after surgery are swelling, new fat or tissue that was never removed. Genuine regrowth needs a new trigger, most often steroids.
Is gyno surgery permanent?
For most men, yes. The removed gland and fat cells do not return. The result can change if you gain a lot of weight, use steroids or start a medicine that causes gynecomastia.
Can gyno grow back after surgery?
Only the tissue left behind can grow, and only if something stimulates it. Surgeons leave a thin layer under the nipple to avoid a crater, and steroids, cannabis or certain medicines can make that layer enlarge.
Can you get gyno again after surgery?
It is possible but uncommon. The risk is highest in men who use steroids after surgery, in men whose original cause was never treated, and where the first operation left gland behind.
Can gyno come back after surgery if you use steroids?
Yes. Steroid users need revision surgery more than three times as often as non-users. If you plan to keep using steroids, discuss this honestly with your surgeon before surgery.
Why is my chest not flat after gyno surgery?
In the first three to six months, it is usually swelling. Later on, it may be fat, scar tissue or tissue left behind. If it has not improved by six months, book a review.
Is gynecomastia permanent if you do not have surgery?
Pubertal gyno often settles on its own, but gyno that has been present for more than a year or two usually becomes fibrous and permanent. Our guide to whether gynecomastia goes away on its own explains more.
Why Choose Centre for Surgery for Gynecomastia Surgery?
We treat every grade of gynecomastia, including grade 3 to 4 and revision cases after surgery elsewhere, with VASER or power-assisted liposuction and gland removal matched to your chest. Surgery is performed by GMC-registered plastic surgeons at our CQC-regulated hospital at 95–97 Baker Street, which has been caring for patients for over 10 years, and the surgeon who examines you at consultation is the surgeon who performs your operation and reviews you afterwards. Our guide to gynecomastia grades explains how the operation is planned, and our gynecomastia surgery cost guide explains the price. When you are asleep, your anaesthetic is TIVA given by a consultant anaesthetist, and almost all of our operations are day cases. We recommend a two-week cooling-off period before any surgery, and we publish our clinical outcomes and patient safety data.
Finance is available through Chrysalis Finance, subject to status. See our finance options page for details.
Phone: 020 7993 4849 | Address: 95–97 Baker Street, Marylebone, London W1U 6RN
Contact us to schedule a consultation
References
- Prasetyono TOH, Andromeda I, Budhipramono AG. Approach to gynecomastia and pseudogynecomastia surgical techniques and its outcome: a systematic review. Journal of Plastic, Reconstructive & Aesthetic Surgery 2022;75(5):1704–1728. doi:10.1016/j.bjps.2022.02.008 ↗
- Fricke A, Lehner GM, Stark GB, Penna V. Gynecomastia: histological appearance in different age groups. Journal of Plastic Surgery and Hand Surgery 2018;52(3):166–171. doi:10.1080/2000656X.2017.1372291 ↗
- Tettamanzi M, Filigheddu E, Ziani F, et al. Optimizing gynecomastia correction surgery: efficacy and safety of tumescent local anesthesia approach. Aesthetic Plastic Surgery 2024;48(23):5067–5073. doi:10.1007/s00266-024-04404-4 ↗
- Vojvodic M, Xu FZ, Cai R, Roy M, Fielding JC. Anabolic-androgenic steroid use among gynecomastia patients: prevalence and relevance to surgical management. Annals of Plastic Surgery 2019;83(3):258–263. doi:10.1097/SAP.0000000000001850 ↗
- Smit DL, Buijs MM, de Hon O, den Heijer M, de Ronde W. Positive and negative side effects of androgen abuse. The HAARLEM study: a one-year prospective cohort study in 100 men. Scandinavian Journal of Medicine & Science in Sports 2021;31(2):427–438. doi:10.1111/sms.13843 ↗
- Kanakis GA, Nordkap L, Bang AK, et al. EAA clinical practice guidelines: gynecomastia evaluation and management. Andrology 2019;7(6):778–793. doi:10.1111/andr.12636 ↗
- Klinger M, Bandi V, Giannasi S, et al. Gynecomastia: ultrasound-confirmed classification pertainent to surgical correction. Aesthetic Plastic Surgery 2021;45(4):1397–1403. doi:10.1007/s00266-021-02187-6 ↗







