



In this guide9 sections
Should Glands Be Addressed During a Neck Lift?
A neck lift, or platysmaplasty, rejuvenates the neck by improving its contour — addressing loose skin, excess fat and the visible banding caused by the platysma muscle. For most people that is the whole operation.
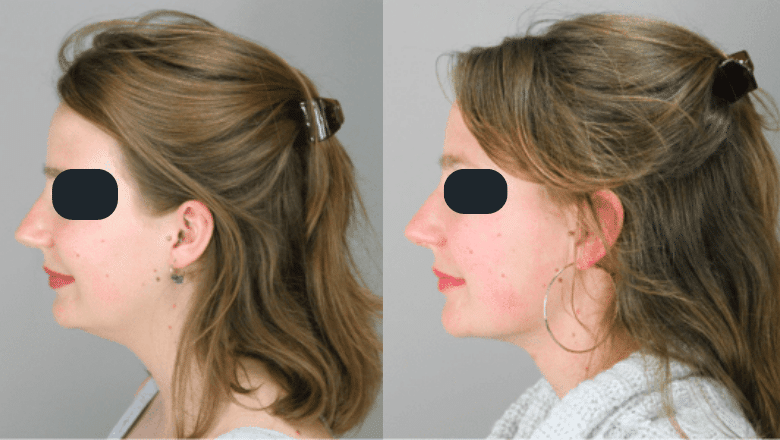
For a minority, it is not. Where the submandibular salivary glands sit low or are prominent, they create a bulge beneath the jaw that skin and muscle tightening will not correct — and can occasionally make more obvious, by tightening the tissue over the top of it. Submandibular gland reduction is the technique that addresses this specific problem, and it is one of the more debated aspects of neck lift surgery.
It is not part of a routine neck lift, and most patients do not need it.
The Anatomy
The submandibular glands sit beneath the jawline on either side, producing much of the saliva in the mouth. They are a normal structure, present in everyone.
Their size does not usually change with age. What changes is the tissue around them — as the platysma muscle loosens and the overlying soft tissue thins, a gland that was always there becomes visible as a rounded fullness below the jawline. Some people also simply have glands that sit lower or are larger to begin with.
This is why the distinction matters clinically: a bulge below the jaw may be fat, a lax muscle, or a gland, and each needs something different. Fat responds to liposuction, muscle laxity to platysmaplasty, and a prominent gland to neither.
Submandibular Gland Reduction — How It Works
Gland reduction is performed through the same incisions used for the neck lift itself, usually beneath the chin or around the ear. Once the deeper layers are exposed, the surgeon identifies the gland and removes only the portion contributing to the visible bulge — typically the outermost, most superficial part.
This is a partial resection, not removal of the gland. Roughly 30–40% of the gland’s volume is taken, leaving the remainder to continue functioning normally.
Why precision matters here
The area around the submandibular gland is anatomically busy. The facial artery and vein run close by, as do the marginal mandibular nerve, which controls the lower lip, the lingual nerve, which supplies sensation to the tongue, and the hypoglossal nerve, which controls tongue movement.
Injury to any of these produces a functional problem rather than a cosmetic one, which is why this is a technique for surgeons who perform it regularly rather than an add-on to be requested casually.
Risks of Gland Reduction
Beyond the usual risks of neck lift surgery, gland reduction carries its own:
- Bleeding. The gland is well vascularised, and haematoma risk is higher when it has been operated on.
- Nerve injury — marginal mandibular, lingual or hypoglossal. Uncommon, but the consequences are functional rather than aesthetic.
- Salivary leak or fistula — saliva escaping from the cut surface of the gland. Usually settles with conservative management.
- Reduced saliva flow. Most people notice no lasting change, since the remaining gland tissue and the other salivary glands compensate. A temporary reduction can occur.
- Over-resection, producing a hollow or uneven contour beneath the jaw.
- Irreversibility. Removed gland tissue cannot be replaced. This is the single most important point to weigh before agreeing to it.
The Clinical Debate
Surgeons genuinely disagree about this, and it is worth understanding both positions rather than being presented with only one.
The case for. Where a prominent gland is the actual cause of fullness beneath the jaw, no amount of skin or muscle tightening will address it. A patient in that position who has a standard neck lift may be disappointed with an otherwise technically good result — the neck is tighter, but the bulge remains.
The case against. It introduces functional risk into an aesthetic operation, it is irreversible, and the aesthetic gain is often modest relative to that risk. Many surgeons take the view that a well-executed deep-plane neck lift with platysmal work addresses the great majority of cases without touching the gland at all.
Our position is that it should be uncommon. Most patients presenting with fullness below the jaw have fat, laxity or both, and gland reduction is appropriate only where examination establishes the gland itself is genuinely responsible.
How to Tell Whether the Gland Is the Problem
This is assessed at consultation rather than by self-examination, but broadly:
- Fat is soft, diffuse, and can usually be pinched between finger and thumb.
- Platysmal banding appears as vertical cords that become more obvious when you tense the neck — see platysmal bands.
- A prominent gland is a discrete, firmer, rounded fullness sitting in a fixed position just below the jawline, which does not change when the neck is tensed and cannot be pinched.
Imaging is occasionally used where the diagnosis is uncertain, and any gland that is tender, changing in size, or fluctuating with meals should be assessed medically rather than cosmetically — those features suggest stones or infection, which are ENT problems, not surgical-aesthetic ones.
Alternatives
Most necks are better served by something other than gland reduction.
- Neck and chin liposuction where submental fat is the cause — see neck liposuction vs neck lift.
- Platysmaplasty where muscle laxity or banding is responsible — see neck lift vs platysmaplasty.
- Deep-plane neck lift technique, which repositions tissue more thoroughly and reduces how much a gland shows without removing any of it. See types of neck lift surgery.
- Energy-based tightening such as FaceTite or Argo Plasma for mild laxity — see tightening neck skin without surgery.
- Chin augmentation, where a recessed chin is making the whole submental area look fuller than it is.
Neck Lift Surgery at Centre for Surgery
Neck lift surgery is performed by GMC-registered plastic surgeons at our CQC-registered facility on Baker Street, rated Good overall, as a day case under TIVA.
At consultation your surgeon will establish whether gland prominence is genuinely contributing to your neck contour, and will say plainly where a standard neck lift achieves what you are hoping for without it. See neck lift before and after photos and neck lift cost.
- Phone: 020 7993 4849
- Email: contact@centreforsurgery.com
- Address: 95-97 Baker Street, London W1U 6RN
Finance options through Chrysalis Finance are available.
Submandibular Gland Reduction: Frequently Asked Questions
What is submandibular gland reduction?
Partial removal of the outer portion of the submandibular salivary gland during a neck lift, where the gland itself is creating a visible bulge beneath the jawline that skin and muscle tightening will not correct. Typically 30–40% of the gland is removed.
Do I need it?
Probably not. Most fullness beneath the jaw is fat, muscle laxity or both, and both respond to standard neck lift techniques. Gland reduction is appropriate only where examination establishes the gland is genuinely responsible.
Will it reduce my saliva production?
Most people notice no lasting change. The remaining gland tissue and the other salivary glands compensate. A temporary reduction can occur and usually settles.
Is it reversible?
No. Gland tissue that has been removed cannot be replaced, which is why the decision should be made carefully and not as an afterthought during the consultation for something else.
What are the specific risks?
Bleeding, salivary leak, and injury to the marginal mandibular, lingual or hypoglossal nerves — affecting the lower lip or tongue. All are uncommon, but they are functional rather than cosmetic risks, which is what distinguishes this from most aesthetic surgery.
How long is recovery?
Broadly the same as a neck lift — gentle activity within one to two weeks, fuller recovery at four to six. Swelling in the submandibular area can take slightly longer to settle.
Will there be extra scarring?
No. The same incisions used for the neck lift give access to the gland, so no additional scars are created.
Can the bulge come back?
The portion removed does not regrow. Where the underlying issue was partly tissue laxity rather than the gland alone, continued ageing can allow some fullness to reappear over time.
What if my gland is swollen or painful?
That is a medical problem, not a cosmetic one. Tenderness, fluctuating size, or swelling that worsens around meals suggests salivary stones or infection and needs assessment by an ENT specialist rather than treatment as part of cosmetic surgery.
Related Articles
- Neck Lift Surgery
- Types of Neck Lift Surgery
- Neck Lift vs Platysmaplasty
- Platysmal Bands
- Neck Liposuction vs Neck Lift
- Risks of Neck Lift Surgery



