



In this guide9 sections
Alar rim retraction is an upward pull of the nostril rim, so that more of the nostril opening shows than it should. In profile it reads as excessive nostril show; from the front the nostril looks angular or triangular rather than smoothly curved. A retracted alar rim is one of the more difficult problems in nasal surgery to correct well, and one of the easier ones to cause.
That second point is the honest heart of this page. Alar retraction is overwhelmingly a consequence of previous rhinoplasty — specifically, of removing too much of the cartilage that holds the rim down. It occurs in a minority of people as a congenital feature, and occasionally after injury, but the great majority of retracted alar rims were created in an operating theatre.
This guide covers how to tell whether you have it, the measurement that defines it, what causes it, the graft techniques used to lower a retracted rim, and — the part the previous version of this page promised and did not deliver — how it is avoided in the first place.
What Alar Rim Retraction Looks Like
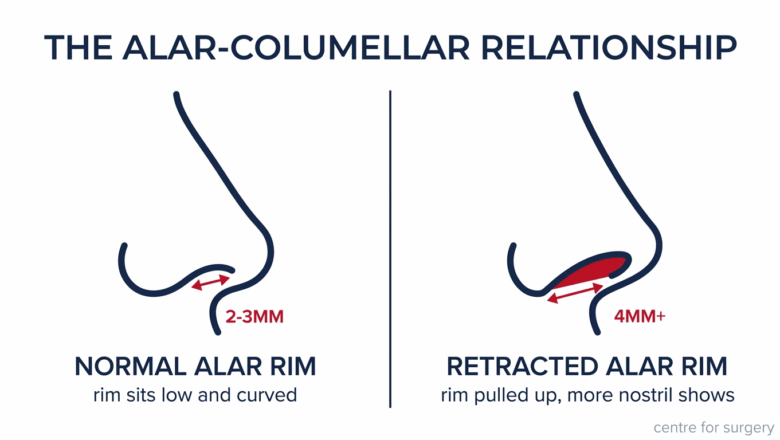
The defining measurement is the alar-columellar relationship — the gap, seen in profile, between the nostril rim and the columella, which is the strip of skin dividing the nostrils.
- 2 to 3mm is the normal range. The rim sits low, curves smoothly, and the nostril opening is largely hidden.
- 4mm or more is retraction. The rim has pulled upward, opening a visible gap and exposing the nostril.
This is genuinely checkable at home. Take a true side-on photograph in even light, without smiling, and look at the space between the nostril rim and the columella. If it looks like a wide crescent rather than a narrow sliver, that is retraction.
Associated features include a nostril that appears vertically oval or triangular rather than a smooth teardrop, visible scalloping or notching along the rim, an apparently shortened nose, and asymmetry where one side has retracted more than the other.
Retraction versus a naturally high rim
Some people simply have a higher alar rim than average, without any surgery, and it is a normal anatomical variant rather than a defect. The distinction matters because congenital high rims are more forgiving to correct — the tissue is soft and has not scarred or contracted — while post-surgical retraction involves scarred, foreshortened lining that resists being brought back down.
If your rim has always looked like that and it does not bother you, there is nothing here that needs fixing.
Why the Alar Rim Retracts
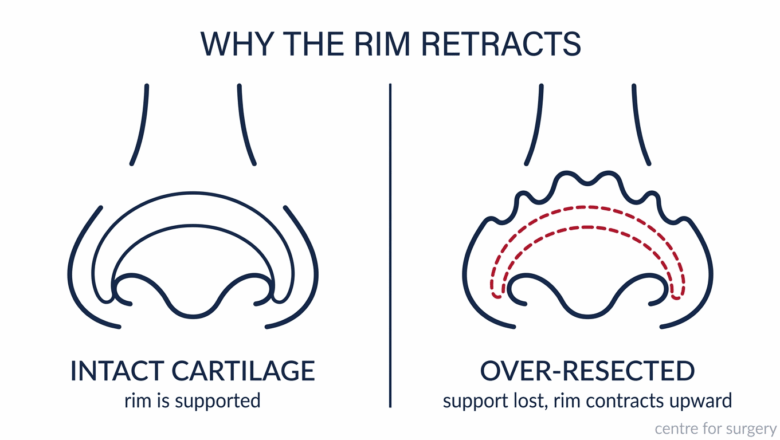
The nostril rim is held in position by the lateral crus of the lower lateral cartilage — a curved band running from the tip out towards the cheek. It is the strut that keeps the rim low and the nostril shape smooth. Remove or weaken it and the rim contracts upward as healing progresses, because there is nothing left to resist the pull of scar tissue.
Previous rhinoplasty
The dominant cause, and it takes several forms:
- Over-resection of the lateral crus. Aggressive trimming to refine a bulbous tip is the classic mechanism. Where less than roughly 6mm of lateral crus is left, the rim loses reliable support.
- Excision of the rim itself in an attempt to reduce nostril show — which produces the opposite result as the wound contracts.
- Excessive cephalic trim — removing the upper portion of the lateral crus, which is a standard manoeuvre taken too far.
- Over-rotation of the tip, which lifts the rim as a secondary consequence even where the cartilage is intact.
- Scar contracture of the nasal lining, particularly where the internal lining was breached or is deficient. This is the hardest version to correct, because there is a shortage of lining as well as of support.
Retraction typically becomes apparent between three and twelve months after surgery, as scar matures and contracts. It is not usually visible immediately.
Other causes
Congenital — a naturally high rim with a short or weak lateral crus, present from birth and often familial. Trauma — injury to the nostril rim or lower lateral cartilage healing with contracture. Ageing — cartilage weakening can modestly increase nostril show over decades, though rarely to a degree anyone describes as retraction. Inflammatory or infective damage to the nostril lining, such as nasal vestibulitis, uncommon but recognised.
Does It Affect Breathing?
It can, and this is worth checking rather than assuming.
The same lateral crural weakness that lets the rim ride up also leaves the sidewall unsupported, so retraction and external nasal valve collapse frequently occur together. If your nostril also draws inward when you breathe in hard, the airway is involved and correction should address both — the same grafts often improve appearance and function simultaneously.
A retracted rim on its own, with a stable sidewall, usually causes no breathing difficulty.
How a Retracted Alar Rim Is Lowered
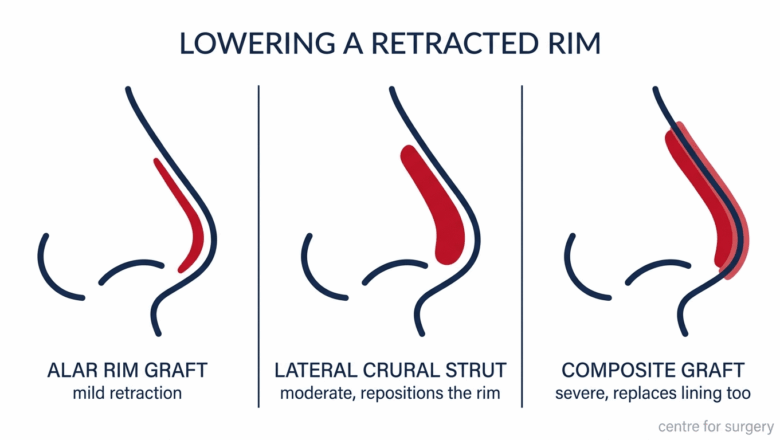
Correction means rebuilding support and, in more severe cases, replacing lining that is no longer there. The technique escalates with severity.
Alar rim graft — mild retraction
A thin strip of cartilage placed in a pocket just inside the nostril rim, running along it. It does not attach to the existing cartilage; it acts as a batten holding the rim down and smoothing contour irregularities. Usually taken from the septum or ear.
Effective for mild retraction of 1 to 2mm beyond normal and for rim notching. Low morbidity, and often placed at primary rhinoplasty as a preventive measure.
Lateral crural strut graft — moderate retraction
A more substantial graft placed beneath the lateral crus, between the cartilage and the lining, which allows the whole rim to be repositioned downward and outward rather than simply supported where it sits. This is the workhorse for genuine post-surgical retraction and also corrects sidewall collapse.
Composite graft — severe retraction
Where the internal lining is short as well as the cartilage — typical after aggressive resection or scarring — support alone cannot pull the rim down, because there is not enough lining to allow it. A composite graft takes cartilage with its attached skin, almost always from the concha of the ear, and replaces both layers at once.
This is effective and it is the most demanding option. Composite grafts can contract, may need revision, and the ear donor site leaves a scar. Expect a longer, less predictable recovery than the other two.
Non-surgical options
Limited, and worth being straightforward about. A small amount of dermal filler placed along the rim can soften mild retraction and improve contour, and it is reasonable for someone wanting improvement without surgery or wanting to preview a change. It lasts 12 to 18 months, it adds bulk rather than repositioning anything, and it cannot bring a genuinely retracted rim down. The nostril rim is also a region where injection requires real care because of the vascular anatomy.
There is no exercise, taping, massage or device that lowers a retracted alar rim.
Timing and recovery
Correction is not attempted before 12 months after the original rhinoplasty, and 12 to 18 months is more usual, because scar must mature before the true position is known and before grafted tissue will settle predictably.
Recovery is comparable to revision rhinoplasty generally: swelling settling over two to three weeks, return to work within a week to ten days, full activity at four to six weeks, and a final result at 12 to 18 months. Where a composite graft has been used, the grafted area passes through a period of looking congested and discoloured before settling.
Results are good but rarely perfect. Retraction is a tissue-deficit problem, and correcting a deficit is harder than correcting an excess — a point worth hearing before surgery rather than after.
How Alar Rim Retraction Is Avoided
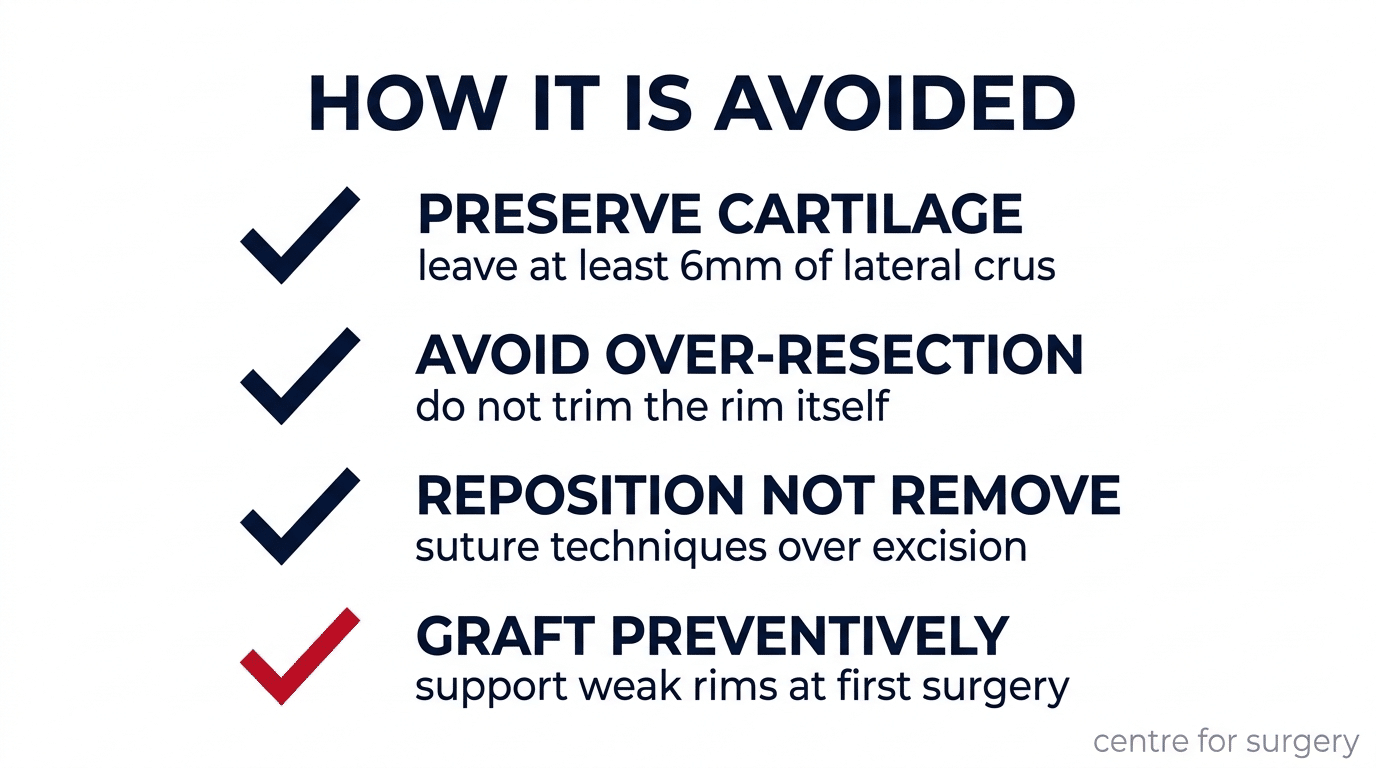
This is the most useful section if you have not yet had surgery, because prevention is considerably easier than correction.
- Preserve adequate lateral crus. Contemporary practice leaves at least 6mm intact. Aggressive cephalic trimming to achieve tip refinement is the single commonest route to retraction.
- Never resect the rim itself. Attempting to reduce nostril show by removing rim tissue reliably makes it worse once the wound contracts.
- Reposition rather than remove. Suture techniques and repositioning of the lateral crus achieve tip refinement without sacrificing support. This is the central principle behind the shift toward preservation rhinoplasty.
- Graft preventively where the rim is weak. Placing an alar rim graft at the first operation, in someone with a naturally weak or high rim, costs little and prevents a difficult problem.
- Respect the lining. Preserving internal lining preserves the option of lowering the rim later.
If you are choosing a surgeon for a first rhinoplasty and your concern is a bulbous or wide tip, asking how they plan to refine it without over-resecting the lateral crus is a question that will tell you a good deal.
Cost
Correcting a retracted alar rim is revision surgery and priced accordingly. Cost depends on the graft required — a rim graft is considerably less involved than a composite graft with a donor site — on whether other elements of the nose are being addressed at the same time, and on the anaesthetic.
Your exact cost is confirmed in writing after in-person consultation and examination. We assess a significant number of patients seeking correction of surgery performed elsewhere and will give you an honest account of what is achievable. Finance is available through Chrysalis Finance, subject to status — see our finance options.
Correction of purely cosmetic retraction is not available on the NHS. Where there is documented functional obstruction, assessment may be.
Frequently Asked Questions: Alar Rim Retraction
What is alar rim retraction?
An upward pull of the nostril rim so that more of the nostril opening shows than normal. Measured as the alar-columellar relationship in profile — 2 to 3mm is normal, 4mm or more indicates retraction.
How do I know if I have a retracted alar rim?
Take a true side-on photograph in even light. Look at the gap between the nostril rim and the columella. A narrow sliver is normal; a wide crescent exposing the nostril suggests retraction. Notching along the rim and a triangular rather than teardrop nostril shape are also indicators.
What causes alar retraction?
Overwhelmingly previous rhinoplasty — specifically over-resection of the lateral crus of the lower lateral cartilage, excision of the rim itself, excessive cephalic trim, over-rotation of the tip, or contracture of the nasal lining. Less commonly it is congenital or follows injury.
Can alar rim retraction be corrected?
Yes, using cartilage grafts. Mild retraction is treated with an alar rim graft, moderate with a lateral crural strut graft, and severe retraction with a composite graft that replaces cartilage and lining together. Results are good but rarely perfect.
What is a composite graft?
Cartilage taken with its attached skin, almost always from the concha of the ear, used where the nostril lining is short as well as the cartilage. Without replacing lining, a severely retracted rim cannot be brought down. It is the most demanding of the graft options and can contract.
How long after rhinoplasty can retraction be corrected?
Not before 12 months, and 12 to 18 months is more usual. Scar must mature before the true rim position is known and before a graft will settle predictably.
Can filler fix a retracted alar rim?
It can soften mild retraction and improve contour for 12 to 18 months, but it adds bulk rather than repositioning the rim and will not correct genuine retraction. Injection at the nostril rim requires particular care because of the vascular anatomy.
Will alar retraction get worse over time?
Post-surgical retraction typically develops over the first three to twelve months as scar contracts, then stabilises. It does not usually progress after that. Age-related cartilage weakening can modestly increase nostril show over decades.
Does a retracted alar rim affect breathing?
Sometimes. The same weakness of the lateral crus can leave the sidewall unsupported, so retraction and external nasal valve collapse often occur together. If the nostril also draws inward on hard inspiration, the airway is involved and both should be corrected together.
Is a high alar rim always a problem?
No. Some people naturally have a higher rim, and it is a normal variant. Congenital high rims are also easier to correct than post-surgical retraction, because the tissue has not scarred or shortened.
Can alar retraction be prevented during rhinoplasty?
Largely, yes. Preserving at least 6mm of lateral crus, never resecting the rim itself, using suture repositioning rather than excision for tip refinement, and placing a preventive rim graft where the rim is weak all substantially reduce the risk.
Why does the rim look notched as well as high?
Notching usually reflects an irregular edge left after cartilage resection, or scar contracture pulling unevenly. An alar rim graft addresses both the height and the contour irregularity.
Is correction covered if my original surgery was elsewhere?
It is assessed and quoted as a new case. We see a considerable number of patients in this position and will tell you honestly what can and cannot be improved.
Assessment at Centre for Surgery
Assessment of a retracted alar rim covers the measurement, the cause, the state of the internal lining, and whether the nasal airway is also affected — because that determines which graft is appropriate and whether lining needs replacing.
Where your rim has always been high and is not causing you difficulty, we will say that surgery is not warranted. Where retraction is post-surgical and severe, we will be explicit that correction improves rather than perfects, and that a composite graft carries a less predictable recovery than people expect.
Our ENT surgeon and rhinologist assesses the nasal airway alongside the appearance, so that correction does not compromise breathing and any existing valve collapse is addressed at the same time.
All surgery is performed by GMC-registered surgeons at our own day-surgery facility at 95–97 Baker Street, Marylebone. We are regulated by the Care Quality Commission and rated Good overall. We recommend a two-week cooling-off period before any surgery is booked.
Patient reviews
You can read our reviews in full on Google Reviews ↗, or on our own patient reviews page. We are rated 4.6 on Google.
Book a consultation
Phone: 020 7993 4849
Email: contact@centreforsurgery.com
Address: 95–97 Baker Street, Marylebone, London W1U 6RN
Contact us to schedule your consultation
Your initial in-person consultation fee is redeemable against the cost of surgery if you proceed.
Related Reading
- Revision rhinoplasty
- Polly beak deformity
- Nasal valve collapse
- Saddle nose deformity
- Flared nostrils
- Alar base reduction (alarplasty)
- Bulbous nose tips
- Preservation rhinoplasty
- Nose shapes: the common types
- Rhinoplasty grafts explained







