


In this guide14 sections
- Key Points
- Are Big Areolas Normal?
- What Is the Average Areola Size? An Areola Size Chart
- Why Are My Areolas So Big? The Main Causes
- Why Are My Areolas Getting Bigger When I’m Not Pregnant?
- When Should You See a GP About Your Areola?
- Do Darker Areolas Look Bigger?
- Large Areolas in Men
- How to Reduce Areola Size Naturally: Does Anything Work?
- Areola Reduction Surgery: What Does It Involve?
- Areola Size After a Breast Lift, Reduction or Augmentation
- Frequently Asked Questions
- Areola Reduction at Centre for Surgery
- References
Key Points
- Large areolas are normal. Areola size varies widely between people, and there is no agreed medical cut-off for a “large” areola.
- The average is about 4 cm across in women. Studies have measured averages of 4.0 cm and 4.5 cm in women. Men’s areolas are smaller, at around 2 to 3 cm.
- Areolas change size through life. Puberty, pregnancy, breastfeeding, weight gain and age can all make them larger.
- Creams and exercises do not shrink them. No cream, exercise or massage has been shown to make areolas smaller. Areola reduction surgery is the only reliable way to reduce their size.
- New changes in one areola need a GP check. See a GP about a rash that does not settle, a nipple that has newly turned inwards, nipple discharge when you are not breastfeeding, or a lump.
Big areolas are common and normal. The areola, the ring of darker skin around the nipple, varies widely in size, colour and shape from one person to the next, and there is no agreed medical definition of a normal range[1]. In a study that measured 600 breasts in 300 adult women, the average areola was 4.0 cm across[2]. There is no fixed cut-off for a large areola: in practice, the term describes an areola noticeably wider than this average, or one that looks big in proportion to the breast.
People search for this in many different words, from “large areolas” to “huge areolas”, but the questions are much the same: is this normal, why has it happened, and can it be changed? This guide covers average areola size (with a simple size chart), the causes of large areolas in women and men, the changes worth showing a GP, and what areola reduction surgery involves if the size bothers you. A large areola is not the same as a puffy nipple, where the areola is raised into a soft dome, although the two can occur together.
Are Big Areolas Normal?
Yes. Large areolas are a normal variation in both women and men, and on their own they are not a sign of a health problem. Areola size tends to follow breast size, it changes at different stages of life, and it can differ slightly between the two sides. Your areolas only need a medical check if something changes that is new, affects one side only or comes with other symptoms, which we cover below.
What Is the Average Areola Size? An Areola Size Chart
Areola size is measured as its diameter: the distance across the widest part, from one edge of the darker skin to the other. The studies below measured areolas directly and give a guide to typical sizes.

| Who was measured | Average areola diameter |
|---|---|
| 300 adult women (600 breasts) | 4.0 cm[2] |
| 54 young Saudi women aged 20 to 25 who had not had children | 4.5 cm[3] |
| 100 healthy men aged 20 to 36 | About 2.7 cm wide by 2.0 cm high where oval; 2.3 cm where round[4] |
These are averages, not limits. Each study measured one group of people, and plenty of healthy people measure well above or below these figures. If you want to check your own, stand in front of a mirror and hold a ruler or soft tape measure across the widest part of the areola, from edge to edge of the darker skin.
Proportion matters more than a single number. A 2003 study that measured the breasts of 37 women aged 20 to 64 found that the areola was, on average, about a third of the width of the breast (a ratio of 1 to 3.4), and the nipple about a third of the width of the areola[5]. The authors suggested this proportion of roughly 1 to 3, sometimes summarised as a “rule of thirds”, as a general guide for planning breast surgery. On this basis, a large areola on a large breast can be entirely in proportion.
What is normal is a separate question from what people say they prefer. In an online survey of 1,049 people, designed to represent the US population and using lifelike 3D models, every group favoured the smallest areola shown, 30 mm across[6]. A preference is not a norm, and our guide to what perfect breasts look like explains what studies of breast attractiveness did and did not find.
Why Are My Areolas So Big? The Main Causes
A large areola on its own is not a sign of a medical problem. It reflects the same natural variation that gives people different heights and breast sizes, along with the changes the breasts go through over a lifetime. The main influences are below.
Breast Size and Body Weight
The areola tends to keep in proportion with the breast[5], so larger breasts tend to have larger areolas. Body weight is linked too: in the study of young Saudi women, those with a higher body weight and BMI tended to have wider areolas[3]. When the breasts grow with weight gain, the skin of the breast and areola stretches with them.
Puberty
The areola starts to change early in breast development. In a study of 313 Italian girls, the nipple widened significantly with each stage of breast development, and the authors suggested that a change in nipple and areola size may be an early marker of puberty[7]. Our guide to when breasts stop growing explains the stages of breast development.
Pregnancy and Breastfeeding
Areolas often become larger and darker during pregnancy, and the small bumps around the edge, called Montgomery glands, become more noticeable. Pregnancy can also cause a “secondary areola”, a lighter ring of extra pigment around the original areola that makes the darker area look wider. Doctors regard it, along with other pigment changes such as the dark line that can appear down the middle of the abdomen (linea nigra), as a normal and harmless part of pregnancy[8]. Our guide to breast changes in pregnancy covers what else to expect.
After pregnancy and breastfeeding, areolas may become smaller and lighter again, but they do not always return to how they were. In a study of 234 premenopausal Korean women, mothers who had breastfed had a wider left areola than mothers who had not breastfed[1].
Ageing
Areolas can also change with age. In the same Korean study, the nipple and areola were larger in older age groups[1]. As breast skin loses elasticity and the breast droops, the areola can stretch and sit lower, and it may become paler. Our guide to how breasts change with age explains why.
Tuberous Breasts and a Wide, Puffy Areola
Sometimes a large areola is part of a breast development difference called tuberous (or tubular) breasts. The lower half of the breast is underdeveloped, the crease under the breast sits high, and breast tissue pushes forward into the areola so that it looks wide and puffy. Surgeons describe this as herniation and enlargement of the areola. The condition affects adolescent girls, on one or both sides, and its cause is unknown[9]. Correction reshapes the lower breast as well as reducing the areola[9], which is why it is treated with tuberous breast correction rather than areola reduction alone.
Why Are My Areolas Getting Bigger When I’m Not Pregnant?
Areolas can widen gradually outside pregnancy, over months or years, as the breasts change with weight gain, hormonal changes, ageing or drooping. If there is any chance you could be pregnant, a pregnancy test is a sensible first step, because larger, darker areolas can be an early sign of pregnancy.
A slow change that affects both sides equally and comes with no other symptoms is in keeping with normal breast change. A change in one areola only, or one that comes with a rash, discharge, a lump or a nipple turning inwards, should be checked by a GP.
When Should You See a GP About Your Areola?
Book a GP appointment if you notice any of the following:
- a change in the size, shape or colour of one areola only, especially if it is new
- a red, scaly, crusted, itchy or weeping rash on the nipple or areola that does not settle
- a nipple that has recently turned inwards or changed position
- discharge from the nipple when you are not breastfeeding, particularly if it is bloody or comes from one side
- a lump or thickening in the breast, behind the areola or in the armpit, or puckering or dimpling of the skin
These symptoms do not usually need emergency care, but book a GP appointment promptly so they can be examined. A persistent rash of the nipple and areola that looks like eczema can occasionally be Paget’s disease of the nipple, an uncommon condition linked to an underlying breast cancer[10]. Men should see a GP about a firm or one-sided lump behind the nipple, or any new breast enlargement in adulthood: a European clinical guideline notes that investigation may find an underlying cause in about 45 to 50% of adult men with gynaecomastia[11].
Do Darker Areolas Look Bigger?
They can look more noticeable. A dark areola against lighter skin has a sharp, high-contrast edge that draws the eye, while a pale areola can blend into the surrounding skin so that its edge is harder to see. That can make a darker areola seem larger than a lighter one of the same size, but this is about how visible the edge is, not the true size. If you are unsure, measuring gives the real answer.
Areola colour varies with skin tone and often darkens in pregnancy. Skin-lightening creams sold online have no effect on size, and the skin of the areola is thin and easily irritated, so speak to a GP or dermatologist before using any lightening product on the area.
Large Areolas in Men
Men’s areolas are smaller on average than women’s. In a study of 100 healthy men aged 20 to 36, 91 had an oval nipple-areola complex, averaging about 27 mm wide and 20 mm high, and the 7 with a round one averaged 23 mm across[4]. As in women, size varies from one man to the next.
In teenage boys, a larger or puffier areola can be caused by pubertal gynaecomastia (often spelled gynecomastia), a swelling of the breast gland tissue behind the nipple. A European clinical guideline states that it affects about half of boys in mid-puberty and settles on its own within 24 months in more than 90% of cases[11]. In adult men, the areola can be stretched by persistent gynaecomastia or by fat on the chest, as our guide to puffy nipples explains. Where gland tissue persists, gynaecomastia surgery removes it, and a stretched areola can sometimes be reduced at the same time.
How to Reduce Areola Size Naturally: Does Anything Work?
No exercise, massage, diet or cream has been shown to make areolas permanently smaller. The areola is skin, and chest exercises work the muscle beneath the breast rather than the areola, so they cannot tighten it. If weight gain has enlarged your breasts, losing weight may make the breasts and areolas a little smaller, but the change varies and stretched skin may not shrink back fully.
What can help is changing how noticeable the areolas are. A bra with moulded or lined cups, or reusable nipple covers, can stop the areola showing through thin clothing. For a lasting reduction in size, surgery is the only reliable option.
Areola Reduction Surgery: What Does It Involve?
Areola reduction makes the areola smaller by removing a ring of pigmented skin from its outer edge. It can be done on both sides, on one side to improve symmetry, or as part of a breast lift, reduction or augmentation. It changes appearance, not health, so the decision is a personal one.
How Areola Reduction Is Done
The surgeon marks the new, smaller areola, removes the outer ring of darker skin and closes the surrounding breast skin to the new edge. A common method is the circular (doughnut) technique, with a purse-string stitch under the skin to help hold the new size. The scar sits along the edge of the areola, where the change in skin colour helps it blend in, although it does not disappear.
On its own, areola reduction is usually done under local anaesthetic, with or without sedation, as a day case. When it is combined with a larger breast operation, such as a breast lift, reduction or augmentation, it is usually done under TIVA (total intravenous anaesthesia). At Centre for Surgery, areola reduction is carried out by GMC-registered plastic surgeons, and our areola reduction cost guide explains how pricing works.
Recovery After Areola Reduction
Most people go back to light activities within a few days. Your surgeon will tell you how to care for the wound, when any stitches that do not dissolve will be removed, and when you can return to exercise and to wearing an underwired bra. Swelling and redness settle over several weeks, and the scar continues to fade for months afterwards. Following your aftercare instructions helps the scar heal as well as it can.
Areola Reduction Risks
Like any operation, areola reduction carries risks, and your surgeon will go through them with you at consultation. The main ones are:
- Bleeding and infection, as with any surgery.
- Scarring. The scar around the areola can widen, thicken or heal unevenly. After a periareolar breast lift, which leaves a similar scar around the areola, the most common complications involve the areola itself: an enlarged scar, the areola stretching again, and an uneven areola shape[12].
- A change in sensation in the nipple and areola, which can be temporary or permanent.
- Asymmetry. The two areolas may not end up exactly the same size or shape.
- Effects on breastfeeding. Areola reduction removes skin rather than breast tissue, but in breast implant surgery, incisions around the areola have been linked to problems with milk supply. In a 1996 study of 42 women with breast implants, drawn from the records of a hospital breastfeeding support programme, 64% had insufficient milk, compared with under 7% of 42 women without implants, and an incision around the areola was the approach most closely linked to the problem[13]. These figures come from implant surgery, not areola reduction, so they do not show its risk directly. If you plan to breastfeed in future, raise this before surgery so the technique can be chosen with it in mind.


Areola reduction before and after photos. Individual results vary.
Is Areola Reduction Right for You?
People consider areola reduction for different reasons. Some feel self-conscious about the size of their areolas, some find they look out of proportion after pregnancy, breastfeeding or weight change, and some want to even out a difference between the two sides. Surgery can make the areolas smaller and more even, but it cannot make them identical, and it leaves a scar.
It is worth having realistic expectations and taking your time. Check that your surgeon is on the GMC register, ask to see before-and-after photos of their areola reduction patients, and read our guide to how to choose a plastic surgeon. We recommend a two-week cooling-off period between your consultation and surgery.
Areola Size After a Breast Lift, Reduction or Augmentation
A breast lift or breast reduction moves the nipple to a new, higher position on the reshaped breast. The areola is resized as part of the same operation so that it stays in proportion with the new breast. Without that step, a large areola on a smaller or lifted breast can look out of balance, and the nipple can end up pointing downwards.
To mark the new areola, surgeons use a circular ring marker, sometimes called a “cookie cutter”. These range from 38mm to 50mm in diameter. Our surgeons most often use 38mm or 42mm, chosen with you at consultation according to your breast size and the look you want. If you would rather not have a perfectly round areola, the surgeon can draw a bespoke template by hand instead.
After a breast augmentation, the areola can stretch a little as the skin accommodates the implant, which can give a softly oval rather than a perfectly round shape over time. If your areolas are already large, reduction can be done in the same operation as your augmentation.
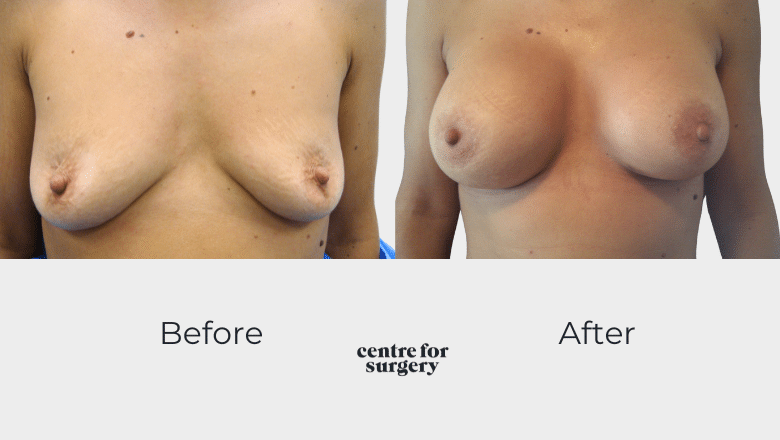


Breast lift before and after photos, including lifts with implants. Individual results vary.
Which breast procedure is right for you?
A few short questions, including a simple mirror test. You will get a suggested procedure, realistic recovery times, and an honest view of when an examination is needed first.
Frequently Asked Questions
Why are my areolas so big?
Large areolas are a normal variation. Areola size tends to follow breast size, and it can increase with puberty, pregnancy, breastfeeding, weight gain and age. A large areola is not a sign of a health problem on its own, but a new change in one areola should be checked by a GP.
What is the average areola size?
In studies that measured areolas directly, the average in adult women was 4.0 cm in a study of 300 women and 4.5 cm in a study of 54 young Saudi women. Men’s areolas are smaller, averaging around 2 to 3 cm. Plenty of healthy people measure well above or below these averages.
Is there an areola size chart I can compare myself to?
There is no official chart that defines a normal areola size. The size chart earlier in this guide gives average measurements from published studies, which make a useful reference point. Areola size also tends to be in proportion to the breast, so a larger breast tends to have a larger areola.
Why are my areolas getting bigger if I’m not pregnant?
Weight gain, hormonal changes, ageing and breast drooping can all make the areolas gradually wider. If there is any chance you could be pregnant, take a pregnancy test. See a GP if only one areola is changing, or if the change comes with a rash, discharge, a lump or a nipple turning inwards.
Can areolas get smaller with weight loss?
They can if losing weight makes your breasts smaller, because areola size tends to follow breast size and body weight. The change varies from person to person, and stretched skin may not shrink back fully.
How can I reduce my areola size naturally?
No cream, exercise, massage or diet has been shown to make areolas permanently smaller. Exercise works the chest muscle beneath the breast, not the skin of the areola, so it cannot tighten it. Areola reduction surgery is the only reliable way to make areolas smaller.
Do darker areolas look bigger than they are?
They can look more noticeable, because a dark areola against lighter skin has a sharper edge than a pale one. That can make it seem larger than a lighter areola of the same size, but it does not change the real size. Measuring across the widest part gives the true figure.
Will my areolas be made smaller during a breast reduction?
Yes. During a breast reduction the areolas are resized so that they sit in proportion with your new, smaller breast. The same applies to a breast lift. Your surgeon will agree the new diameter with you before surgery.
What is the difference between the nipple and the areola?
The nipple is the raised centre of the breast through which milk flows; the areola is the ring of pigmented skin around it. The two are treated differently: areola reduction narrows the pigmented ring, while nipple reduction shortens or narrows the nipple itself. Some patients have both at once.
Areola Reduction at Centre for Surgery
Our plastic surgeons are GMC-registered and have experience in areola reduction and related breast procedures, working with each patient to understand their individual goals and give honest, realistic guidance. Centre for Surgery is a CQC-regulated facility on Baker Street, rated Good overall by the Care Quality Commission.
If you would like to discuss areola reduction, contact us to book a consultation.
References
- Park IY, Kim MR, Jo HH, et al. Association of the nipple-areola complexes with age, parity, and breastfeeding in Korean premenopausal women. Journal of Human Lactation 2014;30(4):474–479. doi:10.1177/0890334414549049
- Sanuki J, Fukuma E, Uchida Y. Morphologic study of nipple-areola complex in 600 breasts. Aesthetic Plastic Surgery 2009;33(3):295–297. doi:10.1007/s00266-008-9194-y
- Al-Qattan MM, Aldakhil SS, Al-Hassan TS, et al. Anthropometric breast measurement: analysis of the average breast in young nulliparous Saudi female population. Plastic and Reconstructive Surgery Global Open 2019;7(8):e2326. doi:10.1097/GOX.0000000000002326
- Beer GM, Budi S, Seifert B, et al. Configuration and localization of the nipple-areola complex in men. Plastic and Reconstructive Surgery 2001;108(7):1947–1952. doi:10.1097/00006534-200112000-00015
- Hauben DJ, Adler N, Silfen R, et al. Breast-areola-nipple proportion. Annals of Plastic Surgery 2003;50(5):510–513. doi:10.1097/01.SAP.0000044145.34573.F0
- Wallner C, Dahlmann V, Montemurro P, et al. The search for the ideal female breast: a nationally representative United-States-census study. Aesthetic Plastic Surgery 2022;46(4):1567–1574. doi:10.1007/s00266-021-02753-y
- De Sanctis V, Elhakim IZ, Soliman AT, et al. Cross-sectional observational study of nipple and areola changes during pubertal development and after menarche in 313 Italian girls. Acta Bio-Medica 2016;87(2):177–183. PMID: 27649000
- Bieber AK, Martires KJ, Stein JA, et al. Pigmentation and pregnancy: knowing what is normal. Obstetrics and Gynecology 2017;129(1):168–173. doi:10.1097/AOG.0000000000001806
- Oroz-Torres J, Pelay-Ruata MJ, Escolán-Gonzalvo N, et al. Correction of tuberous breasts using the unfolded subareolar gland flap. Aesthetic Plastic Surgery 2014;38(4):692–703. doi:10.1007/s00266-014-0340-4
- Seetharam S, Fentiman IS. Paget’s disease of the nipple. Women’s Health 2009;5(4):397–402. doi:10.2217/whe.09.23
- Kanakis GA, Nordkap L, Bang AK, et al. EAA clinical practice guidelines-gynecomastia evaluation and management. Andrology 2019;7(6):778–793. doi:10.1111/andr.12636
- Pelle-Ceravolo M, Angelini M, Ciarrocchi S, et al. The double intradermal continuous suture technique for the round block in periareolar mastopexy. Plastic and Reconstructive Surgery 2026;157(6):855e–859e. doi:10.1097/PRS.0000000000012445
- Hurst NM. Lactation after augmentation mammoplasty. Obstetrics and Gynecology 1996;87(1):30–34. doi:10.1016/0029-7844(95)00349-5

Related Articles
- Options for Cosmetic Breast Reshaping
- Pointy Breasts: Causes and Treatments
- Is a Breast Lift Without Scars Possible?


