


In this guide18 sections
- Key Points
- What Are the Grades of Gynecomastia?
- What Grade of Gynecomastia Do I Have?
- Grade 1 Gynecomastia: Mild Gyno
- Grade 2 Gynecomastia, Including Grade 2a and 2b
- Grade 3 Gynecomastia: Severe With Mild Sagging
- Grade 4 Gynecomastia: Severe With Significant Sagging
- Simon vs Rohrich: Which Gynecomastia Grading Scale Is Used?
- How Common Is Each Grade of Gynecomastia?
- Is It Gyno or Fat? What Grading Does Not Tell You
- Do Gyno Stages Go Away on Their Own?
- Gynecomastia Treatment by Grade
- Gynecomastia Grades Before and After Photos
- What Does My Gynecomastia Grade Not Tell Me?
- Which cosmetic surgery for men is right for you?
- Frequently Asked Questions
- Why Choose Centre for Surgery for Gynecomastia Surgery?
- References
Key Points
- Gynecomastia is graded 1 to 4, and the dividing line is skin rather than size. Grades 1 and 2 have little or no excess skin; Grades 3 and 4 do, and that is what changes the operation.
- Grades, stages, levels and types all mean the same thing. They describe how much tissue there is and whether the skin has stretched, not what the tissue is made of.
- Most men are Grade 1 or 2. In a 2025 series of 960 men, nearly three in five were Grade I or IIa on Simon’s scale, and only one in eight had the most severe grade.
- Grade decides the technique, not whether treatment is worthwhile. Mild gyno is treated as readily as severe; it simply needs less done, usually through a short incision at the edge of the areola.
- Grade does not tell you whether it is gland or fat. That separate question decides whether surgery will help at all.
- Pubertal gyno often settles; adult gyno rarely does. Tissue that has been present for more than one to two years is unlikely to shrink on its own, whatever its grade.
Gynecomastia grades describe how enlarged the male chest is and, more importantly, how much the skin has stretched. Knowing your grade helps you understand what gynecomastia surgery would involve, how long the scar is likely to be and whether mild gyno is worth treating at all. This guide explains the four grades of gyno, the two grading scales surgeons use, how common each stage is, and how each grade is treated, with real before and after photos.
Grading tells you how much tissue there is, not why it formed. Our guide to the causes of gynecomastia explains why it develops, and how common gynecomastia is puts the numbers in context.
What Are the Grades of Gynecomastia?
Gynecomastia is the growth of true glandular breast tissue in men. It is firm, rubbery, sits directly behind the areola, and does not respond to diet and exercise the way fat does, which is why so many men train for years without changing it. It is graded according to how much tissue is present and whether the skin has stretched to accommodate it.
You will see the grades called gyno stages, stages of gyno, gynecomastia levels or types of gynecomastia. They all describe the same scale:
| Grade | What it looks like | Excess skin |
|---|---|---|
| Grade 1: mild | A small button of tissue behind the areola, often just a puffy nipple | None |
| Grade 2: moderate | A fuller chest that shows through a fitted t-shirt, sometimes split into 2a and 2b | None (2a) or minor (2b) |
| Grade 3: severe with mild sagging | A heavy chest that starts to droop towards the crease | Some |
| Grade 4: severe with significant sagging | A clearly feminine contour with a stretched, downward-pointing areola | Marked |

What Grade of Gynecomastia Do I Have?

Stand in front of a mirror with your arms relaxed at your sides and work through it in order. Does your chest tissue sag below the crease beneath it? If not, you are in Grade 1 or 2, and whether it shows through a fitted t-shirt separates the two. If it does sag, does the areola point downward rather than forward? If not, Grade 3; if it does, Grade 4.
This is an orientation rather than a diagnosis. Surgeons assess skin elasticity by pinching and releasing, which you cannot reliably judge on yourself. Two things are worth ruling out before you settle on a grade: pseudogynecomastia, which is fat without glandular tissue and is not graded on this scale at all, and unilateral gynecomastia, where one side is affected and the two sides may grade differently. If the main change is a soft, raised areola rather than a fuller chest, read our guide to puffy nipples.
Grade 1 Gynecomastia: Mild Gyno
A small, localised button of glandular tissue directly behind the areola, with no excess skin and a chest that otherwise looks normal. Often the only visible sign is slight puffiness of the nipple itself, most obvious in cold weather or through thin fabric. This is what most people mean by mild gyno or minor gyno, and it is the commonest reason men reach a page like this. Our guide to what gyno feels like describes the typical firm disc under the nipple.
Is mild gyno normal? Glandular tissue behind the areola is present in a large proportion of men. It only becomes gynecomastia when there is enough to change how the chest looks or feels, and it only becomes a problem when it bothers you.
Does grade 1 gyno go away? If it appeared during puberty and you are still in your teens, quite possibly. The European Academy of Andrology guidelines report that pubertal gynecomastia settles on its own within two years in more than 90% of boys.[1] If it has been present and unchanged for longer than that, it is unlikely to regress without treatment. Our guide to whether gynecomastia goes away on its own explains the timescales.
Will training or grade 1 gyno exercises get rid of it? No. Exercise burns fat, not gland. Building the pectoral muscle beneath glandular tissue can push it forward and make it more prominent, which is why some men find the appearance worsens as they get fitter. Our article on gyno in fit men explains why.
Is it worth treating? Grade 1 gives the most reliable results of any grade, because there is no skin problem to solve. It is usually a small excision at the lower edge of the areola, sometimes with a little liposuction to feather the edges, and the scar sits in the pigment border. If it bothers you, it is treatable; if it does not, nothing needs doing.
Grade 2 Gynecomastia, Including Grade 2a and 2b
More tissue and a visibly fuller chest, but skin that is still largely taut with no meaningful sagging. This is where the chest becomes noticeable in a fitted t-shirt and men start avoiding certain clothes.
Grade 2 is often subdivided, following Simon’s original 1973 classification.[2] Grade 2a has no skin excess at all; grade 2b gynecomastia has minor skin excess. The distinction matters because 2b sits at the threshold where a surgeon starts weighing whether the skin will retract on its own once the tissue beneath it has gone.
Treatment is typically liposuction to reduce the fatty component combined with direct excision of the gland, still through an incision at the edge of the areola. Power-assisted liposuction and VASER liposuction are both used for the fatty component. VASER uses ultrasound energy to loosen dense, fibrous tissue before it is removed, and your surgeon will advise which suits your chest. Liposuction of any kind is limited where there is marked skin excess, which is why skin, rather than the liposuction technology, drives the plan for Grades 3 and 4.[3]
Grade 3 Gynecomastia: Severe With Mild Sagging
A substantial volume of combined glandular and fatty tissue, heavy enough to begin pulling the skin downward. The lower border of the chest starts to droop toward or slightly past the crease, and the areola may begin to stretch.
This is the grade where planning genuinely changes. Removing the tissue alone may leave loose skin behind, so the surgeon has to judge whether the skin will retract or whether some needs removing. That decision depends on your age, skin elasticity, how long the tissue has been present and whether there has been significant weight loss. Our guide to loose skin after gynecomastia surgery covers the question Grade 3 patients most often ask.
Grade 4 Gynecomastia: Severe With Significant Sagging
Marked enlargement with pronounced sagging, a stretched and enlarged areola, and a downward-pointing nipple. The chest has a distinctly feminine contour, and this is what most people mean by severe gynecomastia.
Grade 4 almost always requires skin removal, and often repositioning of the areola. That means longer scars. The trade-off is unavoidable, and any surgeon promising a Grade 4 correction through a small hidden incision is either misjudging the grade or overselling the result. Where significant weight loss came first, the picture overlaps with skin laxity after weight loss rather than gynecomastia alone.
Simon vs Rohrich: Which Gynecomastia Grading Scale Is Used?
Two grading systems are used in practice, which is why you will see gyno described with three grades on some sites and four on others.
- Simon’s classification (1973) has three grades: Grade I small enlargement without skin excess, Grade IIa moderate enlargement without skin excess, Grade IIb moderate enlargement with minor skin excess, and Grade III marked enlargement with excess skin.[2] It remains the scale used in most research papers.
- Rohrich’s classification (2003) has four grades, based on volume and the degree of sagging: Grade I minimal enlargement of under about 250 g without sagging, Grade II moderate enlargement of about 250 to 500 g without sagging, Grade III severe enlargement with mild sagging, and Grade IV severe enlargement with more marked sagging. Each grade is also split into A, mainly glandular, and B, mainly fibrous. The 2003 classification in Plastic and Reconstructive Surgery ↗ was published alongside a series of 61 men, and its authors found ultrasound-assisted liposuction effective for most grades, reserving excision for severe gynecomastia with significant skin excess.[4]
The four grades used by most clinics, including on this page, follow Rohrich’s scale, with Grade 2 sometimes split into 2a and 2b in the way Simon described. Whichever scale is used, the turning point is the same: the moment the skin starts to sag.
How Common Is Each Grade of Gynecomastia?
Most men who have surgery are at the milder end of the scale. In a 2025 multi-centre series of 960 men in Aesthetic Plastic Surgery ↗, 16.7% were Simon Grade I, 41.7% Grade IIa, 29.2% Grade IIb and 12.5% Grade III. All were treated with VASER liposuction and gland removal through a small incision, and minor complications such as bruising, temporary numbness and haematoma occurred in 1.7%.[5] A German series of 217 operated breasts found a similar pattern, with 77% at Grade I to IIa.[6]
In other words, most men worried about their grade do not need the long scars they fear.
Is It Gyno or Fat? What Grading Does Not Tell You

A man with a Grade 2 chest made of fat and a man with a Grade 2 chest made of gland need different operations, and one of them may need no operation at all.
Pinch the tissue directly behind the areola between finger and thumb. A firm, rubbery, well-defined disc that feels distinct from what surrounds it is glandular. Soft tissue that feels the same as the rest of the chest and thins out gradually is fat.
Gland does not respond to weight loss. Fat does. Where the problem is purely fat, the condition is pseudogynecomastia, and it may improve with weight loss alone. Most men have some of both. If you are trying to tell gyno vs no gyno, the full comparison is in our guide to gynecomastia vs chest fat.
Do Gyno Stages Go Away on Their Own?
It depends almost entirely on when it started.
Pubertal gynecomastia frequently resolves. It appears as hormone levels fluctuate in adolescence, and in most cases settles within two years as they stabilise.[1] Operating during this window is usually discouraged for exactly that reason, and our page on teenage gynecomastia explains when surgery is considered.
Adult-onset gynecomastia rarely resolves. Where it develops later, through hormonal change, certain medications, alcohol, anabolic steroid use or an underlying condition, the tissue tends to persist once established. Removing the cause may stop progression but seldom reverses what has already formed, which is why the guidelines suggest surgery for long-lasting gynecomastia that has not regressed.[1]
The rough rule is one to two years. Beyond that, glandular tissue has usually become fibrous and is unlikely to shrink, whichever grade it is. If you are looking for alternatives first, our guide to non-surgical gynecomastia treatments sets out what can and cannot help.
Gynecomastia Treatment by Grade

This is borne out in practice. A 2013 surgical algorithm covering 118 patients and 217 operated breasts ↗ assigned technique strictly by grade: 77% of breasts were Simon Grade I to IIa and treated with gland removal through a half-circle incision at the lower edge of the areola combined with liposuction; 18% were Grade IIb, where skin redundancy meant a skin-tightening step around the areola was added; and 5% were Grade III, requiring a breast-reduction-style operation. The complication rate across the series was 4.1%, and 88% of patients rated the result as good or very good.[6]
Two things follow from those figures. Most gynecomastia is treatable through a short incision at the edge of the areola. And the point at which that changes is not size but skin, exactly as the grading implies. A separate series of high-grade cases in Annals of Plastic Surgery makes the same point from the other direction: in Simon Grade III, liposuction or gland removal without skin excision frequently leaves loose skin that needs a second operation.[7]
- Grades 1 and 2 are treated with liposuction, direct gland excision, or both, through a small incision at the lower border of the areola. No skin is removed, the scar is short and well hidden, and recovery is quick. For lower grades, the pull-through technique removes gland through a very small incision.
- Grade 3 is the judgement call. Sometimes the same approach works and the skin retracts; sometimes skin removal is needed. A surgeon who commits to one before examining you is guessing.
- Grade 4 requires skin reduction and often repositioning of the areola. The contour result can be excellent, but the scars are longer and permanent, and that trade-off must be understood before, not after.
Across every grade, gynecomastia surgery at Centre for Surgery is performed as a day case under TIVA or local anaesthetic, with sedation if you wish. Our guide to anaesthesia for gynecomastia surgery explains which suits which grade. What matters more than grade is that the operation is matched to what your chest is actually made of, and that the surgeon leaves a thin, even layer beneath the areola rather than clearing it, which is what prevents a crater deformity.
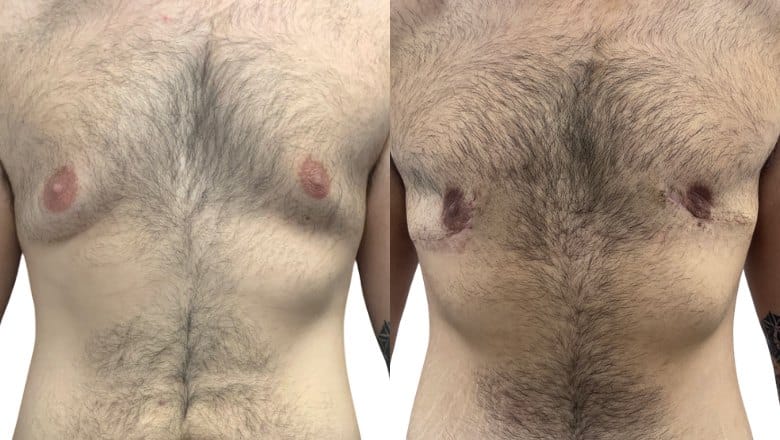
Gynecomastia Grades Before and After Photos
These are real Centre for Surgery patients, shown with their permission. More results are in our gynecomastia before and after photos gallery.


What Does My Gynecomastia Grade Not Tell Me?
- Whether it will bother you. Plenty of men with Grade 3 are untroubled; plenty with Grade 1 are deeply self-conscious. Grade is a description, not a threshold for deserving treatment.
- Whether surgery will help. If the tissue is mostly fat, weight loss may be the better first step regardless of grade.
- What your scar will look like. That depends on your own healing as well as the incision. Our guide to gynecomastia scars explains how they settle.
- How much it will cost. Higher grades take longer and may need skin work, but the range is narrower than people expect. Our guide to gynecomastia surgery cost explains what affects the price, and our page on gynecomastia surgery on the NHS covers funding.
Which cosmetic surgery for men is right for you?
A few short questions, including a simple pinch test if stomach fat is your concern. You will get a suggested procedure, realistic recovery times, and an honest answer if surgery is not what you need.
Frequently Asked Questions
What are the 4 grades of gynecomastia?
Grade 1 is mild enlargement with no excess skin. Grade 2 is moderate enlargement without significant skin excess, sometimes split into 2a and 2b. Grade 3 is severe enlargement with mild sagging. Grade 4 is severe enlargement with significant sagging and a downward-pointing areola.
Does grade 1 gynecomastia go away?
If it started during puberty, often yes, usually within two years. If it began in adulthood or has been unchanged for more than one to two years, it is unlikely to go away without treatment, because the tissue has become fibrous.
What is the difference between grade 2a and 2b gynecomastia?
Grade 2a has no skin excess. Grade 2b has minor skin excess that does not usually need removing. The distinction matters because 2b is the point at which a surgeon starts weighing whether the skin will retract on its own after the tissue has been removed.
Can exercise get rid of mild gyno?
No. Exercise reduces fat, not glandular tissue. Building the chest muscle underneath can push gland forward and make it more visible, which is why some men notice their gyno more as they get fitter.
How do I know if it is mild gyno or fat?
Pinch behind the areola. A firm, rubbery disc with a clear edge is gland; soft tissue that blends into the rest of the chest is fat. Gland does not respond to weight loss.
Can grade 4 gynecomastia be treated without long scars?
Realistically, no. Significant skin excess has to be removed, and removing skin leaves a scar. Any promise of a Grade 4 correction through a small hidden incision should be questioned closely.
What blood tests are used to diagnose gynaecomastia?
Where a doctor thinks tests are needed, the European guidelines suggest testosterone, oestradiol, SHBG, LH, FSH, thyroid function, prolactin, hCG and AFP, plus liver and kidney function.[1] Many men with long-standing pubertal gyno do not need them, but new gyno in an adult usually does.
Will the NHS pay for gyno surgery?
Rarely. Most NHS areas treat gynecomastia surgery as cosmetic and only fund it in exceptional circumstances. Our guide to gynecomastia surgery on the NHS explains the criteria.
What are the downsides of gynecomastia surgery?
Every operation leaves a scar, and higher grades leave longer ones. Other risks include bleeding under the skin, fluid collections, changes in nipple sensation, contour irregularities and, if too much tissue is removed under the areola, a crater deformity. Our guide to gynecomastia recovery explains what to expect.
Why Choose Centre for Surgery for Gynecomastia Surgery?
We treat every grade of gynecomastia, including grade 3 to 4 and revision cases after surgery elsewhere, with VASER or power-assisted liposuction and gland removal matched to your chest. Surgery is performed by GMC-registered plastic surgeons at our CQC-regulated hospital at 95–97 Baker Street, which has been caring for patients for over 10 years, and the surgeon who examines you at consultation is the surgeon who performs your operation. At consultation your surgeon will establish whether the tissue is glandular, fatty or mixed, assess your skin directly, and tell you which technique that combination needs, including when losing weight first would give a better result than operating now. When you are asleep, your anaesthetic is TIVA given by a consultant anaesthetist, and almost all of our operations are day cases. Our other options for men are on our surgery for men page. We recommend a two-week cooling-off period before any surgery, and we publish our clinical outcomes and patient safety data.
Finance is available through Chrysalis Finance, subject to status. See our finance options page for details.
Phone: 020 7993 4849 | Address: 95–97 Baker Street, Marylebone, London W1U 6RN
Contact us to schedule a consultation
References
- Kanakis GA, Nordkap L, Bang AK, et al. EAA clinical practice guidelines: gynecomastia evaluation and management. Andrology 2019;7(6):778–793. doi:10.1111/andr.12636 ↗
- Simon BE, Hoffman S, Kahn S. Classification and surgical correction of gynecomastia. Plastic and Reconstructive Surgery 1973;51(1):48–52. doi:10.1097/00006534-197301000-00009 ↗
- Brown RH, Chang DK, Siy R, Friedman J. Trends in the surgical correction of gynecomastia. Seminars in Plastic Surgery 2015;29(2):122–130. doi:10.1055/s-0035-1549053 ↗
- Rohrich RJ, Ha RY, Kenkel JM, Adams WP. Classification and management of gynecomastia: defining the role of ultrasound-assisted liposuction. Plastic and Reconstructive Surgery 2003;111(2):909–923. doi:10.1097/01.PRS.0000042146.40379.25 ↗
- Ali H. Correction of gynecomastia with combination of ultrasonic liposuction (VASER) and gland excision through a minimal scar incision: a multi-center experience. Aesthetic Plastic Surgery 2025;49(16):4638–4647. doi:10.1007/s00266-025-04801-3 ↗
- Wolter A, Scholz T, Diedrichson J, Liebau J. Surgical treatment of gynecomastia: an algorithm. Handchirurgie, Mikrochirurgie, Plastische Chirurgie 2013;45(2):73–79. doi:10.1055/s-0033-1334910 ↗
- Tashkandi M, Al-Qattan MM, Hassanain JM, Hawary MB, Sultan M. The surgical management of high-grade gynecomastia. Annals of Plastic Surgery 2004;53(1):17–20. doi:10.1097/01.sap.0000112347.30612.f4 ↗







